How the Anion Gap Evaluates
The anion gap is a useful way to assess the difference between measured positively charged ions and measured anions in serum chemistry. In standard acid-base analysis, it assists clinicians in identifying whether an electrolyte imbalance is being linked to unmeasured anions rather than by the ions typically reported on a lab panel. This makes it a helpful diagnostic tool for sorting out a metabolic disturbance.
At its core, the anion gap reflects the relationship between sodium concentration, chloride concentration, and bicarbonate level. Because the body must maintain acid-base balance, shifts in electrolytes can indicate a broader acid-base disorder. That is why the anion gap is often reviewed alongside other laboratory values rather than used alone.
The concept is based on the fact that plasma remains electrically neutral, even though not all ions are measured directly. The reported numbers show an anion-cation difference that indirectly indicates the presence of acids, proteins, and other charged particles. In clinical practice, this is especially useful when the serum bicarbonate is low and the source of the acid load needs clarification.
Because the anion gap is an estimate rather than a direct count, it is best viewed as a screening test with strong screening utility. It does not diagnose a specific disease by itself, but it refines the differential diagnosis and supports clinical interpretation in a patient with suspected metabolic problems.
In what way the Anion Gap Calculator Functions
An anion gap calculator uses standard lab inputs to carry out a fast calculation formula that derives the gap from sodium, chloride, and bicarbonate. The usual formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
This equation compares the key measured cation, serum sodium, with the primary measured anions, serum chloride and serum bicarbonate. The result is used during acid-base analysis to evaluate whether there are extra acids in the blood that are not directly shown on the panel.
Some labs use a variation that includes potassium, but the sodium-based form is the most widely used in clinical review. The calculator is particularly valuable because it eliminates manual arithmetic errors and provides immediate support for clinical evaluation. It is often applied after reviewing a basic metabolic panel or an electrolyte panel.
For example, if the serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the gap is 12. That number may be within the expected reference range, depending on the laboratory’s methodology. The result then informs next steps in evaluating the patient’s acid-base disorder and overall metabolic disturbance.
Because the formula depends on measured lab inputs, the calculator is only as reliable as the numbers used. A small change in sodium, chloride, or bicarbonate can change the result and influence severity assessment. That is why the tool should be used with the full clinical picture, not as a standalone answer.
Typical Anion Gap Range and Interpretation
The usual range for the anion gap varies by laboratory because of multiple analyzers, reporting methods, and reference materials. In most settings, the reference interval is narrow enough that a result above it suggests a elevated anion gap, while a result within it may indicate a standard anion gap pattern. The exact number must always be considered in relation to the lab’s own reference range.
Clinical interpretation begins with determining whether the gap is high, normal, or unexpectedly low. A increased anion gap often suggests accumulation of acids or other unmeasured solutes. A normal gap does not exclude AG formula using Na Cl HCO3 a serious acid-base problem, but it shifts attention toward bicarbonate loss or chloride gain rather than excess acid production.
Albumin is a major contributor to the gap because it behaves as an unmeasured anion. When reduced albumin is present, the measured anion gap may appear falsely low or normal even when there is significant acid accumulation. That is why a raw result must be reviewed carefully, especially in hospitalized or critically ill patients.
In practical terms, the same numeric value can mean different things in different contexts. A gap that is normal by one lab’s standards may be borderline high by another lab’s reference interval. This is why the calculator should be paired with the laboratory’s specific reference range and the patient’s acid-base status.
Reasons of High Anion Gap Metabolic Acidosis
Metabolic acidosis with a high anion gap typically reflects accumulation of acids that consume bicarbonate and leave behind excess anions. This is among the main uses of the anion gap calculator in everyday acid-base analysis. The result helps clinicians separate a classic high-gap pattern from other forms of acidosis.
Lactic acidosis is a common cause and occurs when lactate builds up due to tissue hypoperfusion, shock, severe infection, seizures, or other states of increased anaerobic metabolism. Because lactate is an unmeasured negative ion, the gap rises as bicarbonate falls. In this setting, the anion gap supports recognition of a critical metabolic problem that needs urgent attention.
Ketoacidosis is another major cause, seen in diabetes, starvation, or alcohol-related metabolic stress. Ketone bodies act as unmeasured ions that increase the gap while lowering serum bicarbonate. The pattern can be especially useful when laboratory findings and symptoms suggest an acid load but the cause is not yet obvious.
Renal failure can also produce a high gap because the kidneys are unable to clear organic acids efficiently. As acids accumulate, the anion gap rises and bicarbonate declines. Other causes may include toxins, severe dehydration, or marked tissue breakdown, but lactic acidosis, ketoacidosis, and renal failure are among the key clinical.
In high-gap states, the calculator helps frame the question: is the patient dealing with excess acid production, impaired acid excretion, or another source of metabolic imbalance? That question directs the next steps in evaluation and treatment.
Reasons of Standard Anion Gap Metabolic Acidosis
A normal-gap profile, also known as nonanion gap acidosis, usually suggests bicarbonate has been removed and substituted by chloride. The anion gap stays within the usual range, but the disorder is still present. The key clue is often a decreased bicarbonate with a relatively high chloride, a pattern known as chloride excess.
Bowel losses is a classic trigger because the gastrointestinal tract can lose alkaline fluid. As bicarbonate falls, chloride rises to maintain electrical balance, producing a non-gap acidosis. In this case, the calculator helps support the pattern but does not identify the source on its own.
Renal tubular acidosis is another important reason. Here, the kidneys fail to manage acid or bicarbonate correctly, leading to ongoing acidosis with a normal gap. Different subtypes can present with varied electrolyte findings, but the overall clue remains the same: a decreased bicarbonate with preserved gap size.
Elevated chloride itself is often part of the process because chloride replaces lost bicarbonate in the serum. This is why assessing chloride values alongside the anion gap is essential. A normal-gap acidosis can be missed if the clinician focuses only on the gap and not on the full chemistry panel.
Recognizing a normal-gap pattern is important because treatment varies from high-gap acidosis. The calculator supports the distinction, but the underlying cause must be determined through history, examination, and further laboratory testing.
How to Correct the Anion Gap Using Albumin
Albumin is as one of the key unmeasured anions in the blood, so shifts in serum albumin can substantially alter the anion gap. When hypoalbuminemia is present, the gap may underestimate the severity of acidosis. That is why albumin correction is often recommended in acid-base assessment.
The corrected anion gap modifies the measured value upward when albumin is low. Different correction methods exist, but the goal is the same: adjust for the loss of negative charge from albumin so the result better reflects the true acid burden. This is a practical form of gap correction that improves clinical interpretation.
A common approach is to apply a fixed amount for each decrease in serum albumin below normal. The exact formula may change by institution, but the principle remains stable. If albumin is reduced, the uncorrected number may seem deceptively normal, masking a high anion gap process.
Correcting for albumin is especially helpful in critical illness, liver disease, malnutrition, or any setting where protein levels may be altered. In these cases, the anion gap calculator should be paired with serum albumin so the interpretation reflects the patient’s actual acid-base state. Without that step, the clinical picture may be less accurate.
In short, hypoalbuminemia can conceal a clinically meaningful rise in acids. Albumin correction helps reveal that risk and enhances the accuracy of the corrected anion gap during routine review.
Anion Gap, Delta Gap, and Mixed Disorders
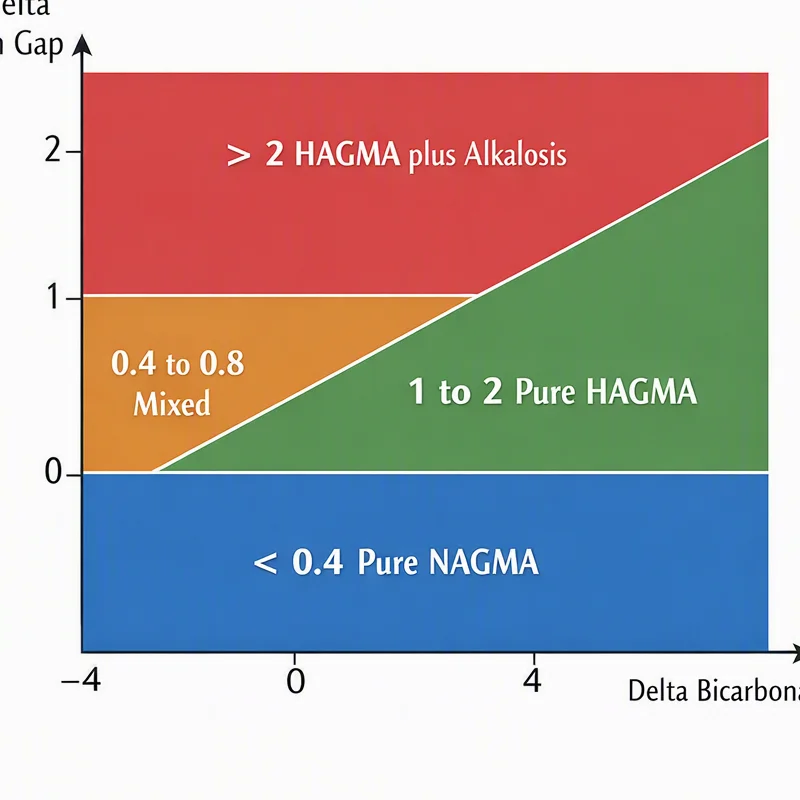
The delta gap and delta-delta relationship are more advanced tools for detecting a combined acid-base disorder. Once a high anion gap acidosis has been found, these calculations help decide whether another disorder is present at the same time. This is especially useful when the patient’s numbers do not follow a single pattern neatly.
The delta gap compares against the rise in the anion gap with the fall in bicarbonate. The bicarbonate difference is used to see whether bicarbonate has fallen proportionally to the gap increase. If the values do not match expected behavior, a second acid-base process may be present, such as metabolic alkalosis or an additional non-gap acidosis.
The delta-delta ratio is another way to assess the relationship between change in the anion gap and change in bicarbonate. A ratio outside the expected pattern can suggest a hidden combined disorder. This matters because a patient may have lactic acidosis plus diarrhea, or ketoacidosis plus vomiting, and the combined findings can obscure the overall picture.
Using delta calculations enhances clinical reasoning because it goes beyond identifying whether the gap is high. It asks whether the acid-base disorder is uncomplicated or layered. That distinction can shape treatment decisions, fluid choice, and the urgency of further testing.
For practical acid-base analysis, the sequence is often: measure the anion gap, decide if it is high or normal, and then apply delta methods if the pattern suggests more than one disturbance.
Using an Anion Gap Calculator for Clinical Review
An anion gap calculator is particularly valuable when interpreting a basic metabolic panel, arterial blood gas, or electrolyte panel in a patient with suspected acidosis. These tests supply the core numbers needed to calculate the gap and judge whether the result aligns with the clinical picture. The calculator is an efficient way to support clinical evaluation when time matters.
It is especially useful when the arterial blood gas shows a low bicarbonate or low pH and the cause is not clear. The calculator can help identify whether the process is a increased anion gap disorder or a normal anion gap process. That distinction reduces the differential diagnosis and helps prioritize further testing.
In everyday practice, the tool is also helpful for reviewing a potential electrolyte disturbance, tracking changes over time, or checking whether treatment is improving the underlying metabolic problem. As lab numbers can shift rapidly, repeated use may support ongoing severity assessment and ongoing monitoring.
The tool must not substitute for your clinical judgment. Instead, it is best used as part of a careful evaluation that considers symptoms, medication review, fluid status, and other test values. In this context, it offers strong screening utility and helps structure the diagnostic process.
Restrictions and Typical Computation Errors
Although its utility, the anion gap has major limitations. Test variability can alter the apparent result because different analyzers and methods generate slightly different values. A number that appears abnormal on one report may fall within the usual normal range on another.
Measurement error can likewise impact the calculation. As the formula depends on serum sodium, serum chloride, and serum bicarbonate, even slight measurement differences can change the outcome. This is a key reason the result should be assessed in the context of the full clinical picture rather than as a standalone value.
Technology used in testing is important too. Ion-selective electrodes are often used to analyze electrolytes, but they are still vulnerable to interference or method differences. Such analytical factors can affect the reported chloride or sodium and thereby influence the final gap.
Another limitation is the presence of unmeasured ions. The anion gap is an approximation, not a direct count of every charged particle in plasma. If unusual substances are present, the calculation may underestimate or overstate the true problem. This is why the tool is best used as a guide for more detailed acid-base analysis, not as the final answer.
Typical errors include ignoring albumin, using the wrong reference range, or failing to consider a mixed disorder. The most reliable approach is to pair the calculation formula with the patient’s symptoms, acid-base status, and complete chemistry results.
Common Questions
What is the purpose of an anion gap calculator?
An anion gap calculator is used to assist with acid-base analysis by estimating whether there is a hidden acid load in the blood. It helps distinguish metabolic acidosis with a high anion gap from a normal anion gap pattern and improves clinical interpretation of laboratory values.
What counts as a normal anion gap?
The normal values depend on the laboratory’s reference range or reference interval. Because different analyzers report slightly different results, the most accurate answer is the one listed by the specific lab. A result within that range usually suggests a normal anion gap, while a higher value may indicate a high anion gap.
How do you compute the anion gap from lab values?
The common calculation formula is: serum sodium − (serum chloride + serum bicarbonate). This uses serum sodium, serum chloride, and serum bicarbonate to estimate the gap. An anion gap calculator automates the math and makes the process faster during clinical review.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because hypoalbuminemia can cause the measured gap appear falsely normal or low. Since albumin is a primary unmeasured anion, albumin correction helps uncover the true corrected anion gap and enhances interpretation in acid-base disorders.
What does a high anion gap indicate in acid-base analysis?
A high anion gap in acid-base analysis usually reflects accumulation of unmeasured anions from a process such as lactic acidosis, ketoacidosis, or renal failure. It is a sign to metabolic acidosis and should lead to review of the patient’s labs, symptoms, and possible mixed disorders.