What’s the Anion Gap?
The anion gap is a computed value that enables clinicians assess acid-base balance and determine causes of metabolic acidosis. It is obtained from a routine electrolyte panel or serum chemistry test and is based on the relationship between serum sodium, serum chloride, and serum bicarbonate. In some formulas, potassium is included as well, though many modern calculations omit it because its contribution is usually limited.
The anion gap shows the difference between measured cations and measured anions in the blood. It is especially useful because not all acids are directly measured. When acid builds up, the body may hold onto unmeasured anions, and the anion gap can help expose that hidden metabolic derangement. This makes it an important part of diagnostic evaluation for patients with suspected acid accumulation.
Clinically, the anion gap is not a diagnosis by itself. Instead, it is a clue that guides the differential diagnosis. A normal or elevated value must always be interpreted in context with the patient’s laboratory values, symptoms, and overall clinical interpretation.
How the Anion Gap Calculator Functions
An Anion Gap Calculator automates the anion gap formula so you can quickly determine whether the result is elevated, normal, or adjusted by albumin. A commonly used formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some calculators add potassium:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
The calculator uses the input values for serum sodium, serum chloride, serum bicarbonate, and occasionally potassium to generate a result that can be compared with the reference interval. This aids clinicians in determining whether the blood chemistry suggests too much unmeasured acids or a different type of acid-base problem.
The calculation is simple, but the meaning is not. A elevated result can indicate added acids in the bloodstream, while a normal result does not rule out acidosis. That is why the calculator is most valuable when paired with the clinical picture, the electrolyte panel, and the rest of the serum chemistry results.
Many calculators also support a corrected anion gap when albumin is low. Because albumin is a negatively charged protein, low levels can make the anion gap appear falsely normal. Including this correction increases the accuracy of clinical interpretation, especially in patients with illness, inflammation, malnutrition, or liver disease.
How to Understand an High Anion Gap
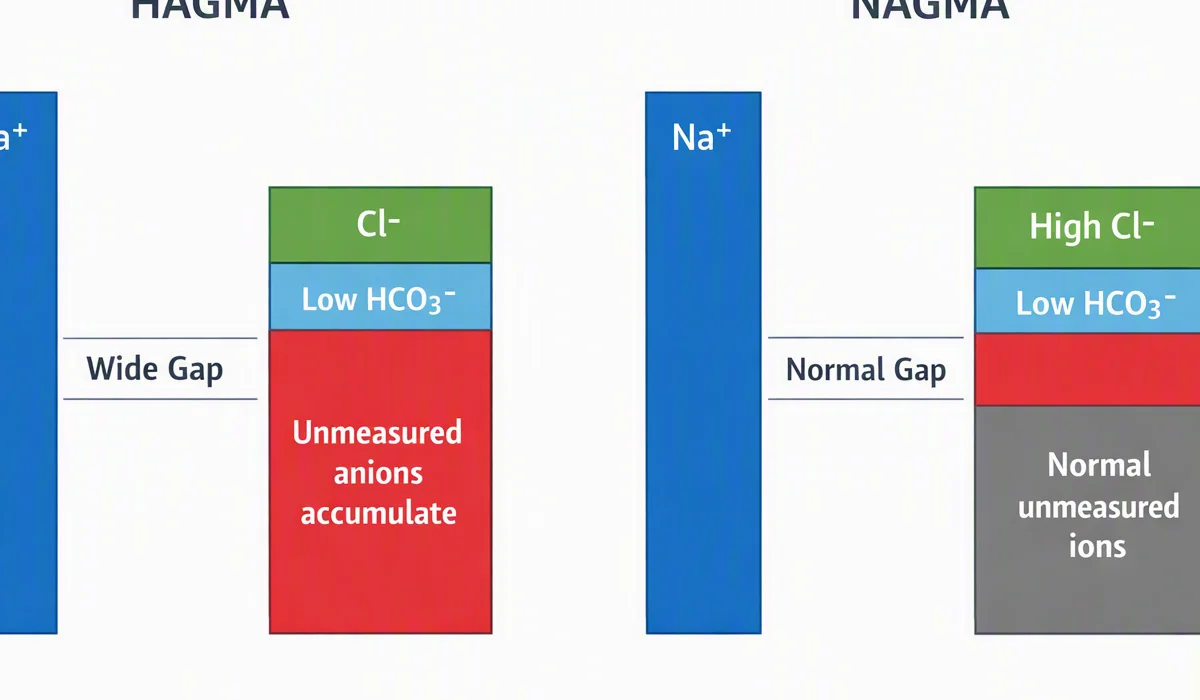
An high result usually suggests high anion gap metabolic acidosis, which means acid has accumulated and increased the amount of unmeasured anions. This pattern often indicates a specific source of acid production or decreased acid clearance.
Typical causes include lactate acidosis, acidosis from ketones, and uremia. In lactic acidosis, tissues create excess lactate during low oxygen states, shock, or severe illness. Ketoacidosis occurs when ketone bodies build up, often in diabetes, starvation, or heavy alcohol use. Uremia develops when the kidneys cannot adequately remove acid and waste products, which is a common issue in advanced kidney dysfunction.
High anion gap metabolic acidosis can also occur with poisoning or toxin exposure. Because the elevated gap represents unmeasured substances, the result can help narrow the differential diagnosis. It does not identify the exact cause on its own, but it guides evaluation toward disorders with acid retention or acid production.
When the result is elevated, it is useful to ask whether respiratory compensation is appropriate. The body often responds to metabolic acidosis by increasing breathing to lower carbon dioxide. If the compensation does not fit the expected pattern, another acid-base disorder may also be present.
Standard Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis is also called hyperchloremic acidosis. In this condition, bicarbonate is consumed, but chloride increases to maintain electroneutrality, so the calculated gap is kept within the expected range. That is why the anion gap can be normal even when metabolic acidosis is clearly present.
A classic cause is diarrhea, which leads to loss of bicarbonate-rich intestinal fluid. Another important cause is renal tubular acidosis, where the kidneys do not effectively acidify urine or retain bicarbonate. In both situations, the problem is not excess unmeasured acids, but a change in measured electrolytes.
This form of acidosis can be overlooked if the clinician focuses only on the gap number and not on the bicarbonate level or overall acid-base balance. If bicarbonate is low and chloride is high, the pattern may still represent significant acidosis even when the calculated gap appears unremarkable.
Recognizing this distinction matters because the treatment and workup vary from those for high anion gap disorders. A careful review of the serum bicarbonate, chloride, and kidney function helps separate hyperchloremic acidosis from acid accumulation due to unmeasured anions.
Modifying the Anion Gap for Serum Albumin
Albumin is among of the main determinants of the anion gap because it has a negative charge and contributes to normal plasma electroneutrality. When albumin is low, the measured anion gap may be deceptively normal. This is why a corrected anion gap is often preferred in patients with hypoalbuminemia.
The correction takes into account the effect of reduced protein binding and the loss of albumin’s negative charge. In practical terms, low albumin can hide a high anion gap metabolic acidosis by making the gap look lower than it truly is. Using a correction factor improves the diagnostic value of the result.
A common approach is to add a fixed amount to the calculated gap for every decrease in albumin below normal. The exact method may differ by institution, but the purpose is the same: refine the number so it better reflects the real burden of unmeasured anions. This is especially important in unstable patients, where hypoalbuminemia is common and metabolic derangement may be severe.
When interpreting a corrected value, remember that albumin influences the buffer system and the measured gap indirectly. A low uncorrected result should not be relieving if the patient is ill and the albumin is reduced. The corrected anion gap can reveal hidden high anion gap metabolic acidosis that would otherwise be missed.
Applying the delta gap to Identify Mixed Disorders
The delta-gap and delta ratio help spot a mixed disorder when elevated anion gap metabolic acidosis is seen. These measures compare the upward change in the anion gap to the fall in bicarbonate, offering insight into whether another disorder is occurring at the same time.
The idea is simple: if the anion gap has increased more than expected relative to the drop in bicarbonate, there may be an additional metabolic alkalosis. If the bicarbonate has fallen more than expected, there may be an additional normal anion gap metabolic acidosis. The delta ratio helps quantify this relationship.
For example, if the anion gap is elevated but bicarbonate is not as low as expected, metabolic alkalosis may be masking part of the acid load. This can happen with vomiting, diuretic use, or other concurrent conditions. Conversely, a very low bicarbonate with only a modest rise in the gap may suggest that more than one acid-base disorder is present.
Using the delta gap is especially helpful in complex diagnostic evaluation. It brings nuance beyond the initial Anion Gap Calculator result and helps explain why some patients do not fit a single textbook pattern.
Main Causes of Metabolic Acidosis
Metabolic acidosis causes of metabolic acidosis are often classified by whether the anion gap is elevated or not elevated. This method strengthens differential diagnosis and assists in identifying the fundamental process quickly.
Major causes of high anion gap metabolic acidosis include toxic alcohols, salicylate poisoning, sepsis, lactic acidosis, ketoacidosis, and uremia. Toxic alcohols can generate acidic metabolites that increase the gap. Salicylate poisoning may produce a complex acid-base picture, at times with respiratory alkalosis and metabolic acidosis together. Sepsis can lead to poor tissue perfusion and lactic acidosis. Chronic kidney disease can advance to uremia, reducing acid clearance and allowing acids to accumulate.
Normal anion gap metabolic acidosis is often the result of diarrhea or renal tubular acidosis, but it can also appear after large-volume saline administration or in other situations where chloride increases as bicarbonate falls. The key point is that both categories represent metabolic acidosis; the anion gap simply helps separate the mechanism.
In practice, clinicians use the gap together with symptoms, medication history, kidney function, and other laboratory values to build a more complete picture. That broader view is often better than any single number.
Limitations of the Anion Gap Calculation
Although the anion gap is helpful, it has important limitations. Laboratory variation can alter the result because different analyzers and methods may give slightly different electrolyte values. This means the reference range may vary across facilities.
Measurement error can also skew the calculation. Even small changes in sodium, chloride, or bicarbonate can change the final number. Since the anion gap is calculated rather than directly measured, it carries any inaccuracy present in the underlying lab tests.
A further limitation is that the gap does not reveal the exact acid involved. A high value may result from lactate, ketones, toxic substances, or retained acids from kidney failure, but the calculator itself cannot differentiate among them. That is why clinical correlation matters.
The osmolar gap is a similar but separate tool that can help assess suspected toxic alcohol exposure. It reflects unmeasured osmoles rather than unmeasured anions. In some poisoning cases, both the osmolar gap and anion gap may be abnormal, but one does not replace the other.
For these factors, the Anion Gap Calculator should be regarded as part of a broader diagnostic evaluation rather than a standalone answer.
When to Seek Urgent Medical Evaluation
Some cases of metabolic acidosis require urgent attention. Profound acidosis can impair organ function and lead to worsening instability if not treated promptly. This is especially concerning when the cause is fast-moving, such as sepsis, poisoning, or severe kidney failure.
Mental status changes is a major warning sign. Confusion, drowsiness, agitation, or reduced responsiveness can reflect severe metabolic derangement or a dangerous underlying cause. These symptoms should not be ignored, especially if they occur alongside abnormal laboratory values.
Watch for signs that respiratory compensation is becoming inadequate. Rapid breathing may initially help correct the acid-base problem, but if breathing becomes exhausted or inadequate, carbon dioxide can rise and the condition can worsen. This is an emergency.
Additionally be alert to electrolyte abnormalities, such as dangerous shifts in potassium, sodium, or bicarbonate. These shifts can affect the heart, muscles, and nervous system. If metabolic acidosis is accompanied by significant symptoms, it should be evaluated promptly by a clinician.
In brief, an abnormal result from an Anion Gap Calculator is not something to panic over by itself, but it should be taken seriously when paired with symptoms, worsening illness, or abnormal vital signs.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to determine the anion gap from routine electrolyte values and help evaluate metabolic acidosis. It assists with clinical interpretation by highlighting whether the pattern suggests high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or a possible mixed acid-base disorder.
What is considered a normal anion gap in metabolic acidosis?
A normal anion gap is a result that falls within the laboratory’s reference interval. Because ranges vary by method and lab, the exact number can differ. In metabolic acidosis, a normal gap anion gap formula with potassium often points toward hyperchloremic acidosis, such as diarrhea or renal tubular acidosis, rather than acid accumulation from unmeasured anions.
How do you correct the anion gap for low albumin?
To correct the anion gap for low albumin, clinicians calculate with a correction factor that adjusts the measured value upward when hypoalbuminemia is present. This accounts for the fact that albumin normally contributes negative charge through protein binding. The corrected anion gap can reveal hidden high anion gap metabolic acidosis that the uncorrected number may miss.
What causes a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, uremia, toxic alcohols, and salicylate poisoning. Sepsis and chronic kidney disease are also important contributors because they can lead to acid accumulation or impaired acid clearance.
Can a typical anion gap actually mean metabolic acidosis?
Certainly. A normal anion gap can still occur with metabolic acid buildup, especially in non-anion gap metabolic acidosis or chloride-related acidosis. Issues such as diarrhea and renal tubular acidosis can decrease bicarbonate while chloride rises, keeping the gap in normal range even though acidosis is there.