What is the anion gap?
The anion gap is a calculated figure used to evaluate acid-base balance by reviewing key measured ions in a serum chemistry or electrolyte panel. An Anion Gap Calculator enables clinicians and learners rapidly judge whether there is an abnormal amount of undetected acids in the blood. Fundamentally, the calculation uses serum sodium, serum chloride, and serum bicarbonate to analyze the relationship between positive ions and negative ions.
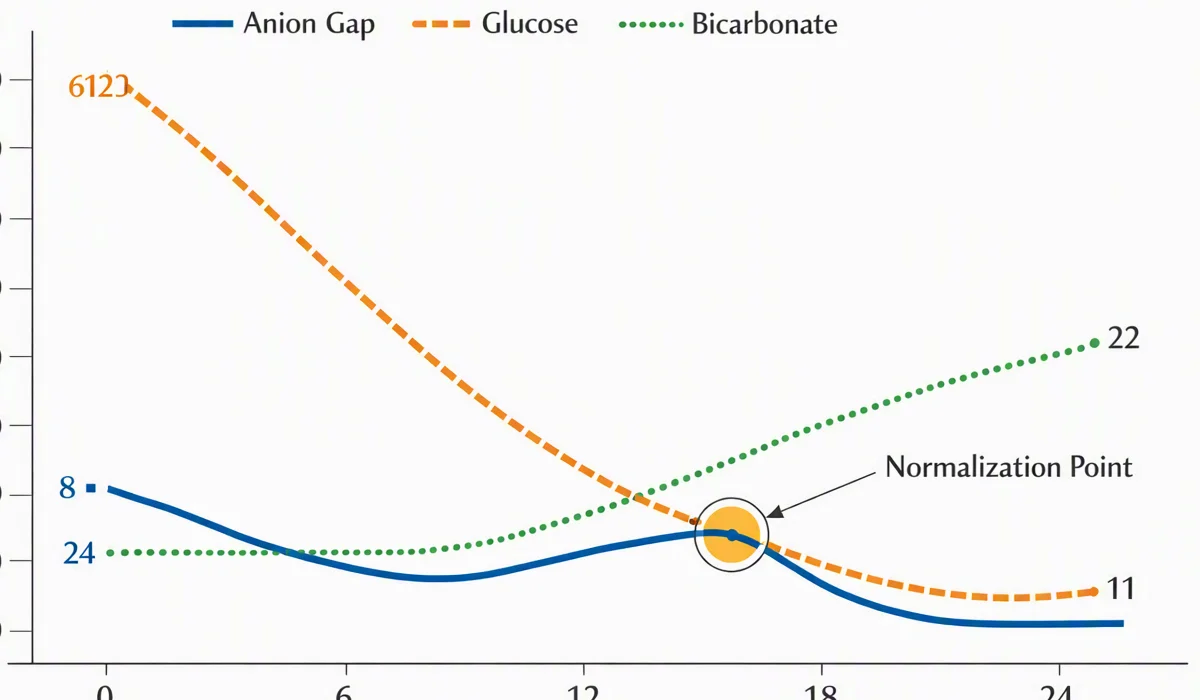
The basic idea is simple: the body keeps electrical neutrality, so the positive and negative charges in blood must remain equal. Because not every ion is directly measured, the anion concentration is derived from routine laboratory values. A shift in this balance can point toward a metabolic disturbance, especially metabolic acidosis. In clinical practice, the anion gap is a fast diagnostic tool for narrowing the cause of an acid-base disorder.
Many clinicians review the anion gap alongside the chloride level, sodium level, and bicarbonate level, then interpret the result in the context of symptoms, medications, and blood gas findings. That broader analysis matters because the anion gap alone does not tell the full story. It is one piece of blood gas interpretation and should be considered with respiratory compensation and the patient’s overall condition.
How the Anion Gap Calculator Works
The classic anion gap formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)This calculation approximates the amount of unmeasured anions in the blood. When sodium is compared with chloride and bicarbonate, the resulting gap represents substances such as proteins, phosphates, sulfates, lactate, and ketones that are not listed directly in the basic panel.
A standard reference range changes by laboratory because methods and instruments differ. That is why clinicians should always interpret the number using the local reference interval rather than relying on a single universal cutoff. The specific reporting method also affects whether potassium is included; most modern calculators omit it for simplicity and consistency.
Many modern calculators also support albumin correction. Albumin is a negatively charged protein and is a major unmeasured anion. If albumin is low, the measured anion gap may appear falsely normal. A corrected anion gap modifies for this by applying a correction factor based on the albumin level, improving clinical accuracy in patients with low protein states.
The result of the calculator is not just a number. It is an initial step for deciding whether the patient likely has high anion gap metabolic acidosis, another type of acid-base disorder, or a mixed pattern. The best interpretation comes from combining the anion gap with bicarbonate level, pH, and the rest of the serum chemistry.
What’s Delta-Delta Analysis?
Delta delta analysis is used to find out whether a patient with a high anion gap also has an additional acid-base disturbance. This approach compares the change in the anion gap to the change in bicarbonate. It helps reveal a mixed acid-base disorder rather than thinking that all abnormalities are explained by a single process.
In a typical case of metabolic acidosis with elevated anions, the extra acid consumes bicarbonate in roughly equal proportion to the rise in unmeasured anions. If the bicarbonate has fallen more than expected, there may be a second process such as normal anion gap metabolic acidosis. If the bicarbonate has fallen less than expected, a concurrent alkalinizing disturbance such as metabolic alkalosis may be present.
This is where delta gap and delta ratio become helpful. The delta gap compares the increase in anion gap to the decrease in bicarbonate. The delta ratio shows that relationship numerically, giving an efficient way to screen for mixed disorders. In practical terms, delta delta helps answer a key question: is the patient’s acid-base pattern explained by a single disturbance, or is more than one problem occurring at once?
Blood gas data often adds important context. Blood gas interpretation can show whether respiratory compensation is appropriate, inadequate, or excessive. That matters because a patient with metabolic acidosis may also have a respiratory issue affecting pH, which changes the overall picture.
Interpreting Delta-Delta Results
To interpret delta delta accurately, begin by determining whether the patient has a high-gap process. Then evaluate the increase in gap with the drop in bicarbonate. The simplest clinical pattern uses the concept of expected bicarbonate. If the bicarbonate is similar to what would be predicted from the increase in anion gap, the disturbance may be a straightforward high anion gap metabolic acidosis. If not, a additional process should be considered.
Here is the logic used in many bedside assessments:
- If the delta gap is around zero, the relationship between anion gap and bicarbonate is aligned. If bicarbonate is less than the expected bicarbonate, consider an added normal anion gap metabolic acidosis. If bicarbonate is higher than expected, think about concurrent metabolic alkalosis or chronic compensation.
In practice, the delta ratio is often used as a rapid method. A decreased ratio suggests that bicarbonate has fallen more than expected for the degree of gap elevation, which supports a mixed picture with non-gap acidosis. A increased ratio suggests smaller bicarbonate loss than expected, which may indicate alkalosis layered on top of a high-gap process.
These findings are especially important because a patient can have normal anion gap metabolic acidosis and high anion gap metabolic acidosis at the same time. The result may appear less dramatic on a single lab printout, yet the underlying acid-base disorder is more complex. Delta delta organizes the interpretation and strengthens clinical decision-making.
Detailed Step-by-Step Illustrative Calculation
Below is a demonstration calculation that shows how an Anion Gap Calculator and delta delta analysis can be used in combination.
Step 1: Examine the laboratory results. Suppose the patient has:
- Sodium: 140 Chloride level: 100 Bicarbonate: 14 Albumin: low enough for correction
Step 2: Determine the anion gap. With the anion gap formula:
140 − (100 + 14) = 26This is elevated and suggests high-gap metabolic acidosis.
Step 3: Apply albumin correction. If albumin is reduced, the measured gap may miss part of the true abnormality. After albumin correction, the corrected anion gap may be even higher. This adjustment is especially helpful when the clinical picture suggests a substantial metabolic disturbance but the raw anion gap is borderline.
Step 4: Calculate the delta anion gap. If the normal baseline gap is 12, the delta anion gap is 26 − 12 = 14.
Step 5: Compare that with bicarbonate loss. If normal bicarbonate is 24, the bicarbonate drop is 24 − 14 = 10.
Step 6: Determine the delta ratio. Delta ratio = 14 / 10 = 1.4.
Interpretation: A ratio around this range often fits a straightforward high-gap metabolic acidosis, without a strong signal for a second major process. However, if the bicarbonate had been much lower than expected, that would suggest an added normal anion gap metabolic acidosis. If the bicarbonate had stayed higher than expected, a concurrent alkalosis would be considered.
In this way, the sample calculation shows more than a number. It links the corrected anion gap, delta anion gap, and serum bicarbonate into anion gap in chronic kidney disease a clinically relevant clinical picture. That is the real value of the calculator: it supports a more nuanced diagnosis rather than a single-label answer.
Common Causes of an Elevated Anion Gap
Various conditions may produce an elevated gap by adding to unmeasured acids in the bloodstream. The most common causes include:
- Lactic acidosis, frequently linked to poor tissue perfusion, severe illness, or increased lactate production Ketoacidosis, that can arise with diabetes, starvation, or alcohol-related states Renal failure, in which acid retention and reduced excretion of unmeasured acids increase the gap Toxic alcohol ingestion, such as substances that generate acid metabolites and profoundly disturb serum chemistry
These causes are often grouped under high-gap states because they produce a form of metabolic acidosis with accumulation of acids that are not reflected directly in standard lab measurements. A careful review of the history, medication list, and blood gas interpretation is essential to separate these causes.
For example, ketoacidosis may present with elevated ketones and profound bicarbonate loss. Lactic acidosis may be seen when the body is under stress and oxygen delivery is impaired. Renal failure can produce progressive acid retention, and toxic alcohol ingestion should always be considered when the clinical setting is suspicious and the acid-base pattern is severe or unexplained.
Limitations plus Clinical Warnings
While an Anion Gap Calculator may assist, it cannot take the place of medical decision-making. A number of issues influence the calculation and must be taken into account during interpretation.
To begin with, albumin correction is crucial because low albumin can conceal an increased gap. Without that adjustment, a patient with significant acid accumulation may look to have a normal value. Second, lab variation can change the reference interval from one instrument to another, so always evaluate the number using the local report. Also, electrolyte abnormalities can distort the apparent balance between sodium, chloride, and bicarbonate, especially in complicated hospitalized patients.
The anion gap also reflects only one part of acid-base balance. A patient can have a near-normal gap and still have a significant disorder. In the same way, respiratory processes can affect pH even when the metabolic component is only somewhat abnormal. That is why the calculator should be used together with blood gas interpretation, symptom review, anion gap formula step by step and other laboratory values.
It is also worth noting that a single snapshot does not always show the whole story. Trends in serum sodium, serum chloride, and serum bicarbonate may be more useful than one isolated draw. In clinical practice, the best use of this tool is to support pattern recognition, not to replace broader diagnostic reasoning.
FAQ
What does an Anion Gap Calculator measure?
An anion gap calculator determines the difference between measured positively charged ions and negative ions, usually using serum sodium, serum chloride, and serum bicarbonate. It approximates the quantity of unmeasured anions and helps identify metabolic acidosis and associated acid-base disorders.
How is delta delta calculated for anion gap interpretation?
Delta delta evaluates the rise in the anion gap to the fall in bicarbonate. Begin by subtracting the normal anion gap from the measured value to get the delta anion gap, then match that number with the drop in bicarbonate from normal. The result helps show whether there is a mixed disorder.
When should albumin correction be used?
Albumin correction should be used when serum albumin is low, because albumin is a major unmeasured anion. Without correction, the corrected anion gap may be underestimated and a clinically important high-gap state may be missed.
What does a high delta delta ratio mean?
A high delta ratio usually means the rise in anion gap is greater than the fall in bicarbonate, which can suggest concurrent metabolic alkalosis or another process that is offsetting the expected bicarbonate loss. It is a clue that the patient may have a mixed acid-base disorder.
Can a normal anion gap happen in a mixed acid-base disorder?
Yes. A patient may have a normal measured gap and still have a mixed acid-base disorder, especially if one process raises the gap while another lowers it, or if the gap is masked by hypoalbuminemia. That is why blood gas interpretation, albumin correction, and the full clinical context matter.