What the Anion Gap Shows
The anion gap is a derived value that helps medical professionals interpret an electrolyte panel by examining the difference between measured plasma ions. It is not listed directly on most lab results, but it can be calculated from the numbers that are already present in routine testing. Because it reflects the difference between major measured cations and anions, it offers an important window into acid-base balance.
An elevated or surprisingly low result can act as a diagnostic clue when reviewing lab results. In practice, the anion gap is most helpful for recognizing an acid-base disorder, especially metabolic acidosis. It also enhances broader clinical interpretation of electrolyte values by indicating hidden acid accumulation, unmeasured ions, or a shift in protein-related charge balance.
An anion gap calculator streamlines this process by turning routine measurements into a quick gap analysis. That can be especially useful when a clinician is reviewing an electrolyte imbalance or trying to connect a chemistry panel with the patient’s symptoms, history, and possible toxin exposure.
Anion Gap Calculator Formula and Values
The main calculation formula relies on the most common blood electrolytes: sodium, chloride, and bicarbonate. In most settings, potassium may also be included, although the simplified formula often excludes it.
A typical version is:
Anion gap = sodium − (chloride + bicarbonate)
In versions that include potassium, the formula becomes:
Anion gap = sodium + potassium − (chloride + bicarbonate)
The specific version used can vary depending on the lab and the reference interval used for interpretation. For this reason an anion gap calculator should always be paired with the lab’s own reporting conventions and the patient’s overall condition.
These inputs matter because they reflect the major measured ions in the sample. Serum sodium represents the dominant measured cation, while serum chloride and serum bicarbonate are major measured anions. The resulting number estimates the amount of unmeasured anions in the blood, which can signal acid accumulation or a shift in protein binding.
How to Work Out Anion Gap Step by Step
To determine the anion gap, use the serum electrolytes from a latest chemistry panel. Typically, these results come from a basic metabolic panel or a comprehensive metabolic panel. Then follow the formula with the numbers reported for sodium, chloride, and bicarbonate.
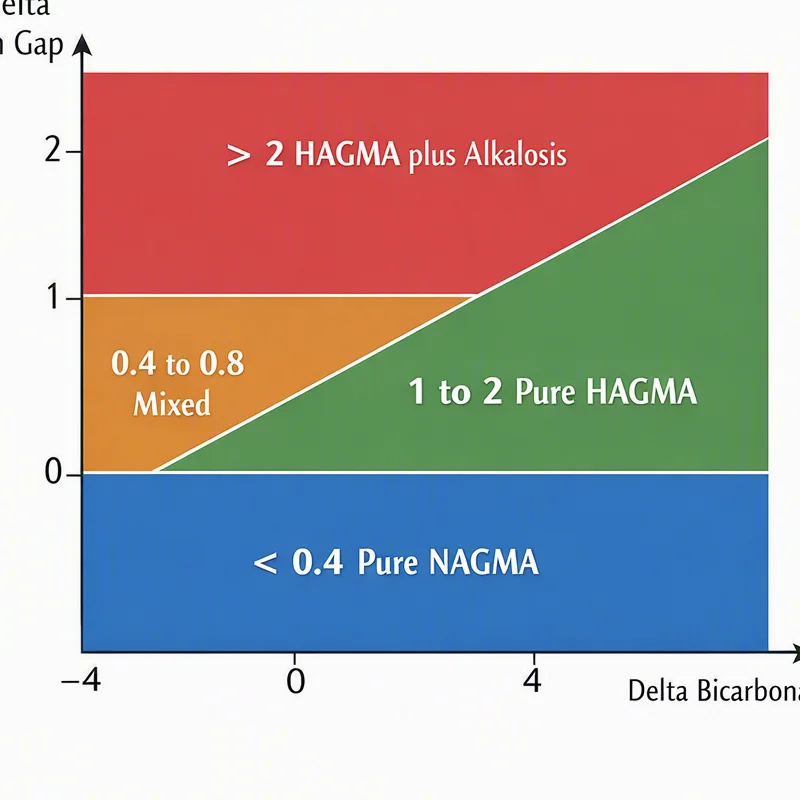
Step by step, the process goes like this:
- Find the reported sodium value. Identify the chloride value. Identify the bicarbonate value. Sum chloride and bicarbonate together. Deduct that total from sodium.
As an example, if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 − (102 + 24) = 14. This result can then be measured against the local normal range.
If potassium is part of the formula used by a specific lab or tool, include it in the sodium side of the equation. Since different panels may report values in slightly different units or formats, unit conversion should always be checked before interpreting the result. A small mismatch in units can create a misleading answer even when the calculation formula is applied correctly.
In clinical use, the calculation is quick, but interpretation is more important than the number alone. The anion gap should be viewed in context with the full set of electrolyte values, the patient’s symptoms, and any sign of an acid-base disorder.
Typical Anion Gap versus High Anion Gap
A standard anion gap usually means the distance between measured cations and anions falls within the expected reference interval. This does not necessarily mean the patient is fine, but it implies there is no obvious increase in unmeasured acids based on the panel alone.
A increased anion gap often points to metabolic acidosis. In this setting, extra acids accumulate in the body, bicarbonate is consumed as it buffers those acids, and the gap rises because the unmeasured anions increase. This is why the anion gap is such a valuable diagnostic clue when analyzing lab results.
In test interpretation, the distinction between normal and high values matters because it guides the next step in evaluation. A high result may prompt review for acid overload, kidney dysfunction, or toxin ingestion. A normal result may shift attention toward bicarbonate loss or chloride gain. Either pattern can reflect a significant metabolic disturbance.
Typical Causes of a High Anion Gap
A high result is frequently linked to multiple important conditions. One of the most familiar causes is lactic acidosis, in which lactate builds up when tissues are poorly perfused or when metabolism is altered. Another major cause is ketoacidosis, where ketone bodies increase during insulin deficiency, starvation, or severe metabolic stress.
Renal failure can also increase the anion gap because impaired kidneys cannot clear acids properly. As renal function declines, acid retention drives acid accumulation and a declining metabolic picture. This is one reason the anion gap is commonly reviewed alongside kidney-related chemistry findings.
Toxic alcohols are another important cause. Ingestion of substances such as methanol or ethylene glycol can result in severe acid-base changes and a dangerously high gap. In this setting, the anion gap becomes a major sign of possible toxin exposure and may require urgent evaluation.
Other high-gap conditions exist as well, but these four are among the key clinical conditions. A careful review of the history, symptoms, and lab results helps determine whether the elevated number is due to poor perfusion, ketone production, renal impairment, or a toxic ingestion.
Frequent Causes of a Normal Anion Gap
A normal anion gap doesn’t exclude a significant problem. It may rather suggest a distinct type of acid-base disturbance, especially one driven by reduced bicarbonate rather than acid excess. One common cause is loose stools, which can lead to considerable loss of bicarbonate from the digestive tract.
Renal tubular acidosis is another important cause. In this condition, the kidneys fail to handle acid and bicarbonate properly, leading to a pattern that often shows a normal anion gap despite ongoing metabolic problems. The issue may be easily missed, but the chemistry pattern is a strong clue.
Loss of bicarbonate from any source can cause this pattern, and that makes bicarbonate depletion critical to the interpretation. To keep electrical neutrality, the body often retains chloride, which leads to hyperchloremia. The result is a normal anion gap with a altered chloride-bicarbonate relationship.
This pattern is sometimes described as hyperchloremic metabolic acidosis. Even though the anion gap remains normal, the patient may still have a meaningful acid-base problem that warrants attention.
Corrected Anion Gap and Albumin
Albumin acts as one of the major unmeasured anions in blood, so its amount can substantially affect the anion gap. When albumin is low, the gap may seem incorrectly normal or only mildly elevated even if a major acid-base problem is present. That is why hypoalbuminemia must always be considered during interpretation.
The corrected anion gap adjusts for low albumin and provides a more accurate view of the patient’s true acid-base state. This process is often called albumin correction. Without it, clinicians may underestimate the severity of the metabolic disturbance.
The reason is related to protein binding. Albumin holds negative charge in the bloodstream, so when albumin drops, the measured gap can narrow even if other acids are present. Correcting for albumin helps expose hidden abnormalities that might otherwise be missed.
For example, a patient with a ostensibly normal gap and marked hypoalbuminemia may actually have a clinically significant high-gap process once the correction is applied. That is why albumin should be reviewed whenever the result does not align with the clinical picture.
When is the time to Use an Anion Gap Calculator
An anion gap calculator is especially helpful whenever a clinician is reviewing an electrolyte panel for indicators of an acid-base problem. It can be used to a basic metabolic panel or a comprehensive metabolic panel, both of which typically include the values needed for the calculation.
It is particularly helpful as a form of clinical decision support when the patient has complaints that could indicate metabolic instability, such as dehydration, altered mental status, unexplained illness, or suspected poisoning. It can also assist in guiding the evaluation of low bicarbonate or other lab abnormalities into a clearer diagnostic pathway.
Because the calculator provides a quick summary of key serum electrolytes, it can support bedside reasoning and inform follow-up testing. Still, it should never replace clinical context. A numeric result is most useful when interpreted with the full picture of lab findings, history, and physical exam.
Constraints and Typical Calculation Errors
Even though https://anion-gap-widget991.opalvector.com/posts/anion-gap-calculator-to-assess-metabolic-acidosis-analysis the formula is simple, several factors can affect accuracy. Lab variability is one issue, since different analyzers and reporting methods can yield somewhat different values. That means two panels from different labs may not match exactly, even when the patient’s condition has not changed.
The chosen reference range also plays a role. What counts as normal in one setting may differ in another, especially if the lab uses a different calculation method or includes potassium. This makes it important to read the result using the correct local standard rather than relying on a single universal cutoff.
Measurement error can occur if a sample is mishandled, diluted, or otherwise compromised. In some cases, a lab artifact may create a misleading result that does not reflect the patient’s true physiology. Repeating the test or comparing it with the broader clinical picture can help identify these issues.
One practical pitfall is assuming that a “normal” number always means there is no problem. Another is forgetting to account for albumin, which can hide a substantial gap. Thorough evaluation of the full panel and awareness of potential error sources improve the quality of interpretation.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is designed to turn an electrolyte panel into a helpful estimate of unmeasured ions in the blood. It helps with clinical interpretation of lab results, especially when evaluating metabolic acidosis, acid accumulation, or an unexpected electrolyte imbalance. It is a practical tool for reviewing sodium, chloride, and bicarbonate together.
How do you calculate anion gap from an electrolyte panel?
Use the calculation formula: sodium minus the sum of chloride and bicarbonate. In some settings, potassium is included as well. The values usually come from serum electrolytes on a basic metabolic panel or comprehensive metabolic panel. After calculating, check the result with the lab’s normal range or reference interval.
How should you interpret a high anion gap mean?
A high anion gap usually suggests metabolic acidosis caused by added acids or unmeasured anions. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result is a important indicator that points toward acid accumulation and helps narrow the differential diagnosis.
In what way does low albumin affect the anion gap?
Low albumin can lower the measured gap because albumin contributes negative charge in blood. With hypoalbuminemia, the apparent result may underestimate the true disorder. A corrected anion gap uses albumin correction to better reflect the actual acid-base balance and avoid missing important abnormalities.
Could a normal anion gap also signal a serious issue?
Absolutely. A normal anion gap in chronic kidney disease anion gap can nevertheless occur with serious conditions such as diarrhea, renal tubular acidosis, or various causes of bicarbonate loss. Hyperchloremia may also be present. So a normal result does not automatically exclude an acid-base imbalance; it only suggests a different pattern of disturbance.