What’s the Anion Gap
This anion gap serves as a computed value derived from serum electrolytes that assists clinicians assess acid-base balance. It relies mainly on sodium, chloride, and bicarbonate levels from a standard electrolyte panel. Because some charged particles are not directly detected in standard blood chemistry testing, the anion gap acts as a useful diagnostic tool for identifying hidden acid accumulation or other forms of metabolic derangement.
An anion gap calculator makes easier this calculation formula and helps turn raw laboratory values into a meaningful clinical clue. In practice, it supports lab interpretation by showing whether there is an excess of unmeasured acids or an unexpected change in measured ions. That makes it especially useful when a patient has symptoms or laboratory values suggesting an acid-base disorder.
The principle is rooted in the balance between positively charged and negatively charged particles in the blood. When the measured cations and anions do not match as expected, the difference suggests an anion deficit or an accumulation of unmeasured substances. This is why the anion gap is so useful in detecting a hidden systemic acidosis.
Common interpretation starts with the serum sodium and serum chloride values, then considers serum bicarbonate. Some calculators also include serum potassium, although many standard formulas omit it. The result is compared with a reference range to determine whether it is normal, elevated, or otherwise unexpected.
How to Determine the Anion Gap
The standard anion gap formula is straightforward. A typical form is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some formulas also include potassium:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Most modern interpretation uses the sodium-based formula because potassium is relatively small in comparison and may not add enough precision to change the clinical picture. However, an anion gap calculator may include both approaches depending on the setting.
Here is how the calculation works conceptually. Sodium is the major measured cation. Chloride and bicarbonate are the major measured anions. Anything left over is the gap, representing unmeasured ions such as proteins, phosphates, organic acids, and other circulating charged substances. A result outside the expected range suggests an unexpected result that should be checked in the context of the patient’s symptoms and other laboratory values.
Albumin matters because it is a major unmeasured anion. When albumin is low, the measured anion gap may appear falsely normal or only mildly elevated. For that reason, many clinicians use an albumin-corrected anion gap to improve accuracy. This correction is especially valuable when evaluating a patient with suspected metabolic acidosis or another acid-base disorder.
A useful way to think about the calculator is that it serves as a quick screening step in blood chemistry analysis. It does not diagnose the underlying cause by itself, but it helps point toward the right next step in medical assessment. In anion gap in chronic kidney disease other words, it is a supportive marker rather than a complete diagnosis.
For example, if sodium is 140, chloride is 100, and bicarbonate is 12, the anion gap is 28. That is higher than the usual reference range and suggests excess unmeasured acids. If albumin is low, the corrected value may be even more informative. This is the sort of calculation that an anion gap calculator can do instantly, reducing the chance of arithmetic mistakes during urgent clinical decision-making.
Why High Anion Gap Metabolic Acidosis Is Important
High anion gap metabolic acidosis is a medically important form of acid buildup in the body in which acids accumulate in the blood and lower the bicarbonate concentration. The gap widens because those acids are not fully captured in standard electrolyte measurements. Identifying this pattern is important because it often reflects a significant underlying cause that needs prompt attention.
From a physiology standpoint, the body tries to preserve acid-base homeostasis by buffering acids and adjusting respiratory and renal function. When that balance is disrupted, acid-base disorders can develop rapidly. High anion gap states often indicate a major metabolic derangement, and the result should be interpreted alongside the patient’s condition rather than in isolation.
One of the most useful clues in this setting is lactate. Elevated lactate can signal tissue hypoperfusion, sepsis, seizures, hypoxia, or other stress states. Because lactate is an unmeasured anion, it can raise the anion gap and point to a potentially dangerous cause of whole-body acidosis.
Recognizing high anion gap metabolic acidosis also improves clinical triage. A markedly elevated gap may indicate a need for rapid reassessment, more testing, or immediate intervention. The calculator therefore supports not only diagnosis but also prioritization, especially when the patient is unstable or has concerning symptoms such as confusion, rapid breathing, vomiting, or decreased level of consciousness.
It is also helpful to remember that not every acidosis is the same. Some disorders produce a normal anion gap, while others produce a high anion gap. Distinguishing between these patterns is a core part of test interpretation and can guide the workup toward a more precise diagnosis.
Common Reasons of High Anion Gap Acidosis
Several situations can result in high anion gap metabolic acidosis. The most common and important in practice include lactic acidosis, ketoacidosis, renal failure, and exposure to toxic alcohols. Every one operates through a different mechanism, but all generate an overabundance of unmeasured acids in the bloodstream.
Lactic acidosis happens when lactate production outpaces clearance. It can be linked to shock, poor perfusion, severe infection, seizures, or certain medications. Because lactate is a supportive marker of tissue stress, it is often checked when a high anion gap is detected.
Ketoacidosis is an additional major cause. In diabetic ketoacidosis, the body breaks down fat for fuel, producing ketones that acidify the blood. Ketoacidosis can also occur with prolonged fasting, heavy alcohol use, or other metabolic conditions. In these cases, the calculator may reveal a marked gap even before the broader picture is fully recognized.
Renal failure can cause acid retention and reduced clearance of organic acids, producing uremia and high anion gap acidosis. As kidney function declines, the body becomes less able to excrete acid and maintain normal chemistry. This is a classic cause of widening blood chemistry abnormalities.
Toxic alcohols are especially important because they are time-sensitive and can be life-threatening. Ethylene glycol and methanol can cause profound acidosis, neurologic injury, and organ damage. A high anion gap in the right context should raise suspicion for these exposures, especially if the history is unclear or the symptoms are severe.
Salicylate poisoning can also produce complex acid-base findings, including an elevated anion gap. It may present with mixed disorders rather than a single pattern, so careful interpretation is essential. In all of these scenarios, the calculator is best used as part of a broader medical assessment rather than as a standalone answer.
How to Read the Result
Reading the result begins with matching it to the expected reference range. A normal anion gap usually suggests that the cause of acidosis, if present, stems from bicarbonate loss or some other non-gap process. A high result indicates extra unmeasured acids and points toward disorders such as lactic acidosis, ketoacidosis, or renal failure.
An albumin-corrected anion gap is particularly important when albumin is reduced. Because albumin plays a major role in the unmeasured anion pool, low levels can mask an elevated gap. Correcting for albumin helps reveal the true corrected value and reduces the chance of missing clinically important acidosis.
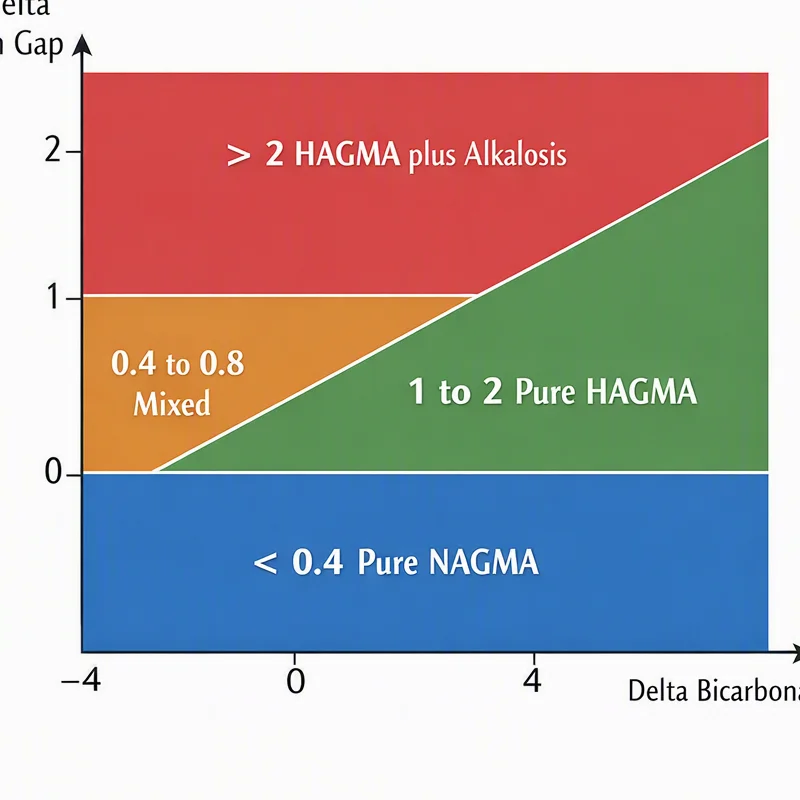
The delta gap is another helpful interpretive tool. It compares the change in the anion gap with the change in bicarbonate, helping detect mixed acid-base states. For example, a patient may have high anion gap acidosis plus another concurrent disorder that alters bicarbonate in a different direction. The delta gap can reveal whether the pattern is isolated or combined.
Interpretation should also account for the patient’s symptoms, medication history, kidney function, glucose level, ketones, lactate, and possible toxin exposure. A calculator result is a starting point for analysis, not the final answer. In clinical practice, the most useful approach is to combine the anion gap with the rest of the electrolyte panel and the overall picture of acid-base balance.
When the result is only slightly elevated, the meaning may depend on lab interpretation, the patient’s baseline values, and whether there is hypoalbuminemia. When the gap is clearly elevated, the likelihood of a significant acid load increases. That is where the calculator becomes an especially valuable diagnostic tool for narrowing the underlying cause.
Limitations of the Anion Gap Calculator
While helpful, the https://anion-gap-reader975.cloudhinter.com/posts/anion-gap-calculator-with-potassium-excluded anion gap calculator is limited. A key issue is lab variation. Separate laboratories may use somewhat different measurement methods, and those differences can change the final number. A value that is normal in one setting may be borderline in another because of how the serum electrolytes are reported.
Measurement error is another issue. Small inaccuracies in serum sodium, serum chloride, or serum bicarbonate can affect the calculated result. This becomes especially important when the value is near the upper or lower end of the expected range. In those cases, repeat testing and clinical context are important.
Hypoalbuminemia can obscure the true degree of acidosis. Since albumin is a major unmeasured anion, low albumin can make the anion gap appear less abnormal than it truly is. That is why an albumin-corrected anion gap often provides a better assessment of the metabolic state.
One more limitation is that the calculator does not explain why the abnormality exists. It may identify the presence of an acid-base problem, but not the precise cause. A high value should always be followed by clinical correlation with symptoms, exam findings, and additional testing. Without that step, there is a risk of overinterpreting a single number.
Finally, the anion gap can be influenced by the broader context of blood chemistry, including medications, fluid status, and chronic disease. The calculator is therefore most useful as part of a complete workup that includes medical assessment and considered review of the entire clinical picture.
When to Seek Prompt Clinical Evaluation
Certain anion gap results should raise rapid concern, particularly if they occur with symptoms of severe acidosis. Severe shortness of breath, confusion, significant weakness, vomiting, chest discomfort, or reduced responsiveness can signal a serious metabolic problem. In such cases, the result may indicate a condition that requires urgent treatment.
Critical values are highly important when the gap is very high or the patient is clinically unstable. An elevated anion gap together with a significant electrolyte imbalance may reflect a toxin exposure, severe infection, uncontrolled diabetes, or kidney failure. These situations can decline quickly.
If there is concern for toxic alcohols such as ethylene glycol or methanol, urgent evaluation is essential. Likewise, salicylate poisoning can cause severe complications and mixed acid-base abnormalities. Delaying care in these settings can worsen outcomes.
Because an elevated gap is a sign of possible systemic acidosis, it should be treated as a significant clue rather than a small lab abnormality. The safest approach is to seek prompt medical review whenever the result is unexpected, severe, or accompanied by worrisome symptoms. The calculator can help identify the problem, but it cannot replace urgent bedside evaluation when needed.
Common Questions
What is the purpose of an anion gap calculator?
An anion gap calculator is used to efficiently check whether a patient has a within-range or elevated anion gap based on standard blood chemistry. It helps with lab interpretation, supports recognition of high anion gap metabolic acidosis, and guides the search for an underlying cause such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure.
How is the anion gap calculated from lab results?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. Some versions also include potassium. A calculator uses serum sodium, serum chloride, serum bicarbonate, and sometimes serum potassium to give a fast and precise result.
Why does the anion gap become high in metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, especially diabetic ketoacidosis, renal failure with uremia, and exposure to toxic alcohols such as ethylene glycol and methanol. Salicylate poisoning can also cause a high anion gap and may produce combined acid-base changes.
Why is albumin correction important in anion gap interpretation?
Albumin is a major unmeasured anion, so low albumin can make the gap look falsely normal. An albumin-corrected anion gap helps show the true abnormality and improves the accuracy of the corrected value. This is especially useful when evaluating suspected metabolic acidosis or other acid-base disorders.
When should a high anion gap result be treated as an emergency?
A high result should be treated urgently when it is paired with critical values, severe acidosis, mental status changes, breathing difficulty, or a major electrolyte imbalance. Suspected poisoning, severe infection, diabetic ketoacidosis, or rapidly worsening kidney failure also warrant immediate emergency evaluation. The overall clinical picture is essential for deciding how urgent the situation is.