What an Anion Gap Indicates
The anion gap is a helpful way to assess the balance between the key ions in blood. It is calculated from serum electrolytes and helps measure the difference between measured cations and measured anions. In practice, the most common values used are sodium, chloride, and bicarbonate, with potassium sometimes included depending on the formula. This basic calculation can reveal important clues about acid-base balance and wider blood chemistry patterns.
Clinically, the anion gap is a diagnostic tool that supports laboratory interpretation of acid base disorders. It does not diagnose a disease by itself, but it helps a healthcare provider focus the possibilities during a metabolic acidosis workup. A change in the gap often suggests unmeasured ions in the bloodstream, which may signal hidden acids or other biochemical shifts.
Because the result is based on routine lab values, the anion gap is simple to obtain from an electrolyte panel. That makes it a practical part of clinical assessment and a rapid way to screen for electrolyte imbalance. Used correctly, it can improve diagnostic accuracy and support better clinical decision making.
How to Use an Anion Gap Calculator with Albumin Level Input
An anion gap calculator including albumin input is designed to offer more than a basic https://anion-gap-estimator828.wpsuo.com/anion-gap-calculator-with-albumin-correction anion gap calculation. It also helps correct for albumin, which is important because low albumin can make the measured result look normal even when an acid problem is present. This is why calculator-style tools that include albumin level are more helpful in practice than a basic formula alone.
To use this type of tool, enter the available input fields from the electrolyte panel, usually sodium, chloride, bicarbonate, and sometimes potassium. Then add the serum albumin value. The calculator uses these lab values to produce both the raw anion gap and the corrected anion gap. That correction can shift the interpretation substantially, especially when the patient has hypoalbuminemia.
The main goal is laboratory interpretation that captures the true physiologic picture. A result that appears normal on first review may become abnormal after albumin correction. That is why the anion gap calculator is more than a convenience tool; it is a diagnostic tool that enhances clinical assessment by adjusting for a common source of error in blood chemistry.
Helpful tip: if the lab report includes sodium, chloride, bicarbonate, and albumin, you already have the core data needed to assess the anion gap more accurately.Anion Gap Formula and Albumin Correction
The standard anion gap formula is expressed as:
Anion gap = sodium - (chloride + bicarbonate)
Certain clinicians use potassium in the calculation, but many everyday references omit it because potassium is present at a much lower concentration and usually changes the result only slightly. Whether potassium is included depends on the local protocol and the specific calculator being used.
Albumin correction is the following step when interpreting the result. Because albumin carries negative charge, lower albumin decreases the measured gap. A common approach is to use a correction for each decrease in albumin from the expected level. This is the essence of albumin correction: it estimates what the gap would have been if serum albumin were normal.
In an albumin adjusted interpretation, a low albumin may mask acid excess. The corrected value gives a more accurate estimate of whether there are extra unmeasured ions in the circulation. That is especially useful helpful when reviewing blood chemistry in complex illness, where the uncorrected result may not reflect the patient’s condition.
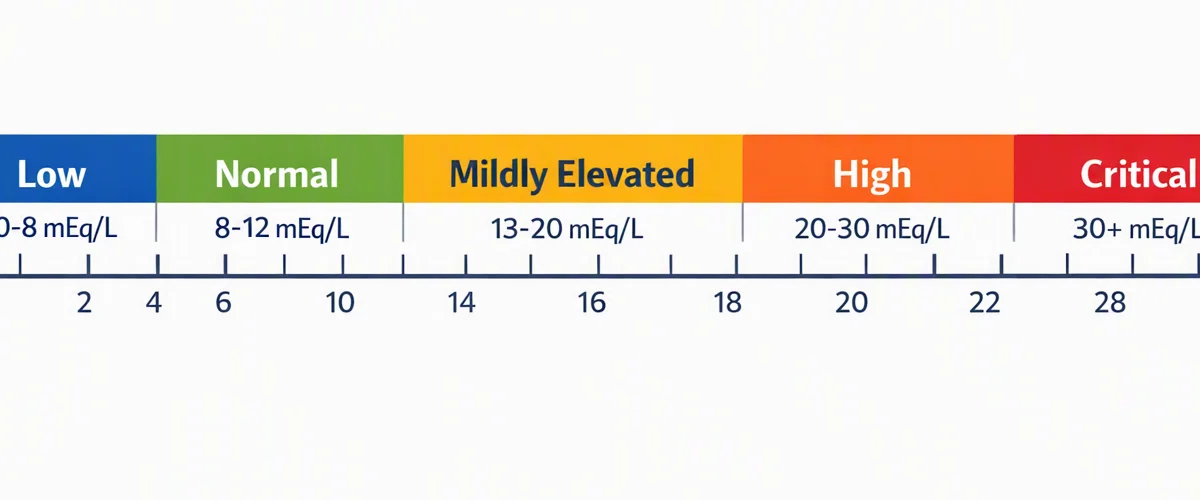
From a clinical standpoint, the formula and correction together help place the number with the broader acid-base balance. They are part of a more complete interpretation guide for metabolic conditions and are particularly valuable when used with the full picture rather than in isolation.
Typical and Unexpected Anion Gap Values
The expected range for the anion gap depends on the lab method and whether potassium is included. As a result, a clinician should always compare the result with the local reference range rather than using a single universal cutoff. Even a small shift in measurement methods can change the expected normal interval.
A high anion gap usually suggests the presence of additional acids or other extra anions. This is commonly associated with anion gap metabolic acidosis. A decreased anion gap is less common, but it can also be clinically meaningful and may reflect laboratory issues, protein abnormalities, or unusual electrolyte patterns.
Because the result varies by method, the best approach is to interpret it in context. A normal value does not always rule out disease, and an abnormal value should not be treated as a standalone diagnosis. The number is most useful when combined with the rest of the electrolyte panel, the patient’s symptoms, and the overall clinical picture.
In short, the anion gap is a clue, not a conclusion. The key is knowing when the value falls outside the expected normal range and whether adjustment for albumin changes the meaning of that result.
Why Albumin Changes the Interpretation
Hypoalbuminemia is a single of the main reasons to adjust the anion gap. Albumin is a negative-charged protein, so it has a strong effect in the body’s normal electrical balance. When albumin falls, the reported gap may fall too, even if the patient has clinically important acidosis.
This happens because albumin is part of the pool of negatively charged substances that help maintain acid-base balance. If albumin decreases, the body responds by altering other ions and the measured gap can become deceptively low or normal. A corrected calculation helps provide a more accurate picture of the underlying chemistry.
Another reason albumin matters is that it helps account for unmeasured anions. When serum albumin is low, fewer negative charges are present in the measured system, so the gap does not reflect the full burden of acids. That can hide important metabolic acidosis and delay recognition of the underlying disorder.
For this reason, an albumin-aware anion gap calculator is more useful for real-world clinical decision making. It increases confidence in the interpretation and helps distinguish true metabolic problems from changes caused by protein levels alone.
Typical Causes of a Increased Anion Gap
A elevated anion gap metabolic acidosis happens when the body retains acids that are not directly measured on a basic electrolyte panel. These acids widen the gap because they replace bicarbonate and contribute additional negative charge from unmeasured anions.
A leading cause is lactic acid buildup, which can develop when tissues do not receive enough oxygen or when metabolism is impaired. Another frequent cause is ketoacidosis, seen when ketone bodies build up in the blood. Both conditions can produce a significantly elevated gap and require prompt evaluation.
Kidney failure is another major cause because the kidneys normally excrete acids. When kidney function declines, acid retention can lead to an increased gap and worsening metabolic acidosis. In each of these situations, the anion gap offers a rapid indication that something is wrong in the body’s handling of acid.
Other causes can include toxic ingestions and less common metabolic conditions, but the main point is the same: an elevated gap signals excess acid or unmeasured negative ions. That is why the result is such a important part of the workup for metabolic acidosis.
Common Causes of a Reduced Anion Gap
A decreased anion gap is less common than a elevated one, but it should not be overlooked. The most frequent explanation is lab error, so retaking the test is often a sensible first step. Sample issues, calibration problems, or reporting mistakes can all cause misleading results.
Another important cause is multiple myeloma. In this condition, abnormal proteins can alter the charge balance in blood and reduce the measured gap. Because these proteins may behave like cations, they can change the expected relationship between the measured ions.
High levels in certain cations can also lower the gap. Hypercalcemia and hypermagnesemia may contribute to a reduced result by shifting the balance of charged particles. Although these are less common explanations, they are clinically important when the low gap is persistent and the rest of the evaluation suggests a real physiologic change.
A low result may also be related to hypoalbuminemia, which is an important reason albumin correction is so useful. Without that adjustment, a patient may appear to have a low or normal gap despite significant underlying acid-base problems.
Clinical Meaning and Follow-up Steps
The most effective way to interpret the result is to consider it in clinical context. The anion gap should be reviewed alongside signs, medical history, current medicines, and the complete electrolyte panel. If the corrected value suggests acidosis, the next step is to find the cause and assess severity.
An effective follow-up tool is the delta-gap, which measures the increase in anion gap to the decrease in bicarbonate. This helps identify whether the patient has just a increased-gap acidosis or a mixed disorder. The delta gap can reveal other acid-base disturbances that are not apparent from a single number.
An arterial blood gas may be necessary to confirm the kind and extent of the acid-base disturbance. It can show the pH, compensatory respiratory response, and whether the patient has a mixed process. When paired with the anion gap and albumin-adjusted interpretation, it provides a much more complete view of the physiology.
When the outcome is unexpected, repeat the test and review the blood chemistry for consistency. If the finding remains abnormal, the clinician should consider further workup for kidney dysfunction, lactic acidosis, ketoacidosis, toxic exposure, protein disorders, or other causes of electrolyte imbalance. The aim is not simply to calculate the number, but to apply it as part of a systematic diagnostic pathway.
In everyday practice, the best approach is easy: calculate the anion gap, account for albumin, measure against the reference range, and then interpret it with the patient’s overall presentation. That process improves diagnostic accuracy and promotes better clinical decisions.
Common Questions
How is the anion gap calculated with albumin level input?
Start with the usual anion gap formula: Na subtracting the sum of chloride and bicarbonate. Then add the albumin level into anion gap calculator so it can perform albumin correction. The result is the adjusted anion gap, which gives a better assessment when serum albumin is low.
Why does low albumin affect the anion gap?
Reduced albumin lowers the number of negatively charged proteins in the blood, which alters acid-base balance and reduces the measured gap. As albumin is one of the main unmeasured anions, hypoalbuminemia can hide a real high-gap problem unless albumin correction is applied.
What would be a normal anion gap after albumin correction?
The normal anion gap after correction depends on the lab’s reference range and whether potassium is included in the formula. A corrected result should be compared with the local reference interval rather than a single universal number. The key is whether the corrected value falls within the expected normal range for that laboratory.
Which conditions cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. These conditions increase unmeasured anions in the blood and lower bicarbonate. Other causes may also exist, so the result should always be interpreted with clinical context and the full electrolyte panel.
At what point should an anion gap result be confirmed with additional testing?
Additional testing is appropriate when the result is unexpected, when lab error is possible, or when the patient has signs of metabolic acidosis. An arterial blood gas, repeat electrolyte panel, and review of albumin can help confirm the finding. Further testing is also warranted if the corrected anion gap suggests a significant acid-base disorder.