Absolutely, dehydration can affect the anion gap, but usually in an indirect way. The main issue is that fluid loss can alter blood volume and cause concentration variations in lab values, which may make the result appear different without necessarily meaning there is a dangerous metabolic problem. An Anion Gap Calculator can help you estimate the number, but clinical interpretation depends on the full picture, including the electrolyte panel, serum bicarbonate, albumin, and symptoms.
The distinction is important. A changed result may reflect simple hemoconcentration from fluid loss, or it may point to a real acid-base issue such as metabolic acidosis. Understanding the difference helps you know when the result is likely temporary and when it needs a closer look.
Understanding the Anion Gap?
The anion gap is a derived value used in blood tests to help evaluate acid-base balance. It is not a measured value. Instead, it reflects the discrepancy between commonly measured ions, especially sodium and chloride, along with bicarbonate in many formulas. This makes it a helpful diagnostic marker for certain types of metabolic disorder.
Simply put, the anion gap helps clinicians identify unmeasured ions in the blood. If the gap is elevated, it can suggest extra acids are present. If it is reduced, it may suggest low protein levels, lab issues, or reduced unmeasured positive ions than usual.
The specific reference range can vary depending on the lab and the method used. That is why clinical interpretation should always use the result from the same testing facility or a trusted medical testing source rather than a one standard number.
The key components behind the calculation are part of routine serum electrolytes. Because these are commonly included in a basic metabolic panel or a broader electrolyte panel, the anion gap is often available even when it is not ordered as a separate test. That makes it a practical tool for reviewing blood chemistry and spotting abnormal results.
How an Anion Gap Calculator Works
An anion gap calculator uses the results from a blood panel to approximate the gap fast. Most calculators depend on sodium, chloride, and serum bicarbonate. Certain formulas also adjust for albumin, because albumin is a major unmeasured anion and can greatly influence the result.
The usual logic is straightforward: the calculator performs an anion calculation by contrasting the measured cations and anions in the sample. When bicarbonate is low, the gap often rises because bicarbonate is being consumed or lost while unmeasured acids accumulate. When albumin is low, the gap may look lower than expected even if the true acid-base state is more involved.
This is why a calculator is helpful, but not complete. It provides a numerical estimate, not a diagnosis. The result must be interpreted alongside the electrolyte panel, the basic metabolic panel, and the patient’s overall condition. In simple terms, the calculator is best used as part of supportive assessment, not as a single answer.
Albumin deserves particular attention. Because it carries negative charge, low albumin can decrease the measured gap. Numerous clinicians will consider a correction when hypoalbuminemia is present, since failing to account for it can hide a important high anion gap.
Can Dehydration Affect the Anion Gap?
Lack of fluids can affect the anion gap, but the effect is often due to fluid loss and more concentrated blood rather than a direct increase in acid production. When plasma volume falls, some blood components become more concentrated. That can change test values on a blood draw and make results look more abnormal than they would after rehydration.
In mild dehydration, the anion gap may not vary much at all. In more pronounced dehydration, especially when accompanied by vomiting, poor intake, or illness, the numbers can move enough to get noticed. However, the key question is whether the change reflects simple electrolyte imbalance or a true metabolic disturbance.
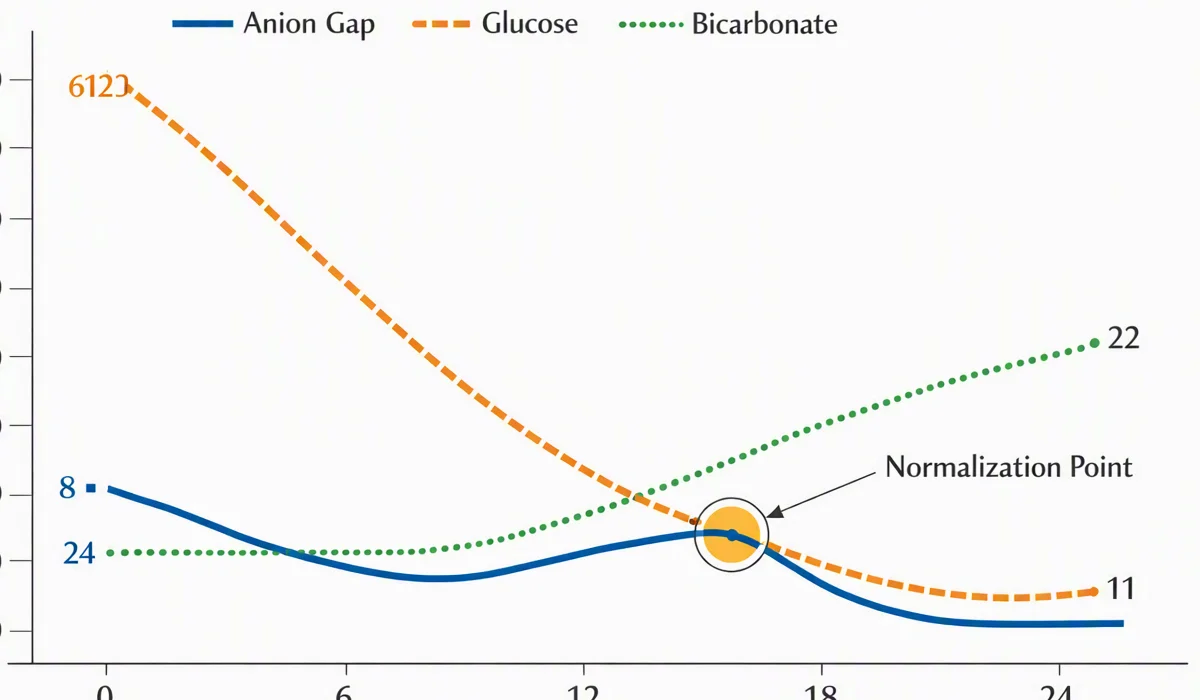
Lack of fluids alone does not usually cause a major raised anion gap. Instead, it may contribute to related problems that raise the gap, such as reduced kidney clearance, lactic acid buildup from poor perfusion, or ketone production if intake is very low. That is why a changed result should prompt the question: what is the underlying cause?
From a practical standpoint, dehydration can also make an already abnormal result look worse. A person with underlying illness may have borderline blood chemistry, and fluid loss can intensify the apparent abnormality. This is where careful results interpretation matters most.
Why Dehydration May Alter Lab Results
A major way dehydration influences testing is through hemoconcentration. As plasma water is reduced, measured substances in the blood can appear more concentrated. It can change lab values across the panel, including sodium, chloride, bicarbonate, and other markers on a basic metabolic panel.
Another important factor is kidney function. The kidneys help balance water, electrolytes, and acid-base status. If dehydration reduces kidney perfusion, the body may briefly retain waste products and alter serum chemistry. For this reason BUN and creatinine are often reviewed together. A higher BUN-to-creatinine pattern can suggest dehydration, though the overall context matters.
Dehydration can also be a clue that the body is under stress from illness, not just lacking water. For instance, vomiting, fever, diarrhea, or poor intake can lead to both fluid loss and metabolic changes. In those situations, the lab pattern may reflect more than simple dehydration, and the anion gap becomes one piece of a larger puzzle.
It is helpful to view the result as part of an integrated review of blood chemistry. If BUN is elevated, creatinine is affected, and the anion gap is abnormal, the pattern may suggest dehydration-related strain on the kidneys or another process altogether. This is where a clinician compares the numbers with symptoms and exam findings.
When a High Anion Gap Is More Worrisome
A raised anion gap is more worrisome when it suggests metabolic acidosis. That indicates acids are piling up in the body faster than they can be removed or buffered. Dehydration may occur alongside this condition, but it is almost never the main explanation when the gap is significantly elevated.
Common causes include lactic acidosis, ketone-related acidosis, and toxic substances. Lactic acidosis can happen when tissues do not get enough oxygen or blood flow, which may occur in serious illness or significant volume depletion. Ketoacidosis can occur with diabetes, prolonged fasting, alcohol use, or very low carbohydrate intake. Certain toxins and medications can also produce a dangerous acid load.
These causes matter because they are true metabolic problems, not just concentration effects from dehydration. A person may be dehydrated and also have one of these conditions. In that case, the dehydration may worsen the issue, but the main concern is the core acid accumulation.
If the anion gap is high, the rest of the panel becomes important. Low serum bicarbonate, a changing chloride pattern, and other signs of electrolyte disturbance can support the diagnosis. The most practical approach is not to focus on one number alone, but to ask whether the pattern fits a known cause of acid-base disturbance.
Reduced Anion Gap: Other Possible Causes
A reduced anion gap is rarer than a raised one, and dehydration is rarely the primary reason. A leading explanation is hypoalbuminemia, since albumin is a major negatively charged protein. If albumin is decreased, the calculated gap can fall even if there is no major acid-base disorder.
Another likely cause is multiple myeloma or other conditions that increase abnormal proteins in the blood. These proteins may behave as positive ions or otherwise shift the balance between measured and unmeasured particles. In such cases, the low gap can be a clue that more testing is needed.
Lab error is also a real issue. Because the anion gap is calculated from several measured values, a small mistake in one input can create a misleading result. Repeating the electrolyte panel or reviewing the sample handling may help if the number does not fit the clinical picture.
When a low result appears, clinicians often review the entire basic metabolic panel, the albumin level, and any signs of protein disorders or medication effects. As with a high result, the goal is to identify the actual cause rather than assuming the calculator result is the diagnosis.
Symptoms That Need Medical Attention
Some signs indicate that a changed anion gap may be part of a more serious illness. Confusion, rapid breathing, and vomiting can occur when the body is dealing with acid-base problems or severe dehydration. Such symptoms need prompt attention, especially if they start fast or worsen.
Severe dehydration can lead to lightheadedness, AG in CKD patients weakness, dry mouth, very dark urine, fainting, and reduced urine output. If severe dehydration is paired with abnormal blood chemistry, the risk of kidney strain and metabolic complications rises. That is why symptom evaluation is just as important as the number itself.
Prompt medical care may be needed when symptoms suggest worsening acid-base imbalance, poor circulation, or inability to keep fluids down. A clinician may order repeat medical testing to check the anion gap, serum bicarbonate, kidney markers, and other data points. The combination of symptoms and lab findings guides the next step.
If you are using an anion gap calculator and the number is abnormal, do not rely on the calculator alone if you feel unwell. Symptoms can reveal a problem that the number only hints at. In that situation, timely medical evaluation is the safest choice.
Common Questions About Dehydration and the Anion Gap
Can dehydration cause a high anion gap?
Dehydration can be associated with a high anion gap, but usually indirectly. Fluid loss can reduce blood volume, cause hemoconcentration, and contribute to kidney stress or poor tissue perfusion. Those changes may raise the gap if they lead to metabolic acidosis, lactic acidosis, or ketone buildup. Dehydration alone is not usually the full explanation.
Can dehydration cause a low anion gap?
Dehydration is not a common cause of a low anion gap. Low results are more often linked to hypoalbuminemia, multiple myeloma, lab error, or other shifts involving positive ions. If dehydration is present, it may affect lab values, but a low gap usually calls for a broader review.
What’s the normal anion gap range?
The anion gap interval varies by the lab, the analyzer, and whether albumin is considered. Most labs use a narrow reference range, but there is no single standard value. For best medical interpretation, compare your result with the range printed on the report and interpret it in the context of the chemistry panel and serum bicarbonate.
Should I drink water before repeating an electrolyte test?
If dehydration may have affected the result, a small amount of water intake may help restore fluid balance balance, but do not assume hydration alone will explain the abnormality. A repeat electrolyte test panel or BMP should be done according to the instructions from your clinician. If you have vomiting, confusion, or trouble keeping fluids down, seek clinical evaluation rather than trying to self-correct the numbers.
When should a changed anion gap be evaluated by a doctor?
A changed result should be evaluated when it is clearly outside the expected normal range, when it comes with symptoms like mental confusion, increased breathing rate, or vomiting, or when there are signs of marked fluid loss or impaired kidney function. A clinician may review blood urea nitrogen, creatinine, serum albumin, and the full blood chemistry to identify the possible cause and decide whether more testing is needed.