Understanding the Anion Gap?
The anion gap is a formula used in acid-base interpretation to assess the amount of unmeasured anions in the blood. It is usually derived from routine serum electrolytes, especially sodium, chloride, and bicarbonate. In simple terms, the anion gap calculator helps clinicians identify whether there are extra acids in the bloodstream that are not directly measured on a standard metabolic panel.
Most of the time, the formula is based on sodium minus chloride and bicarbonate. Because sodium is the main measured cation and chloride and bicarbonate are the main measured anions, the gap reflects the difference between what is measured and what is not. A higher-than-expected result suggests an elevated anion gap, which often points to acid accumulation from conditions that produce organic acids or other unmeasured acid load.
This matters because the anion gap is not a diagnosis by itself. It is a pattern. A high value supports a search for causes of high anion gap metabolic acidosis, but the result must always be interpreted with the rest of the clinical picture, including serum bicarbonate, pH, and the patient’s symptoms.
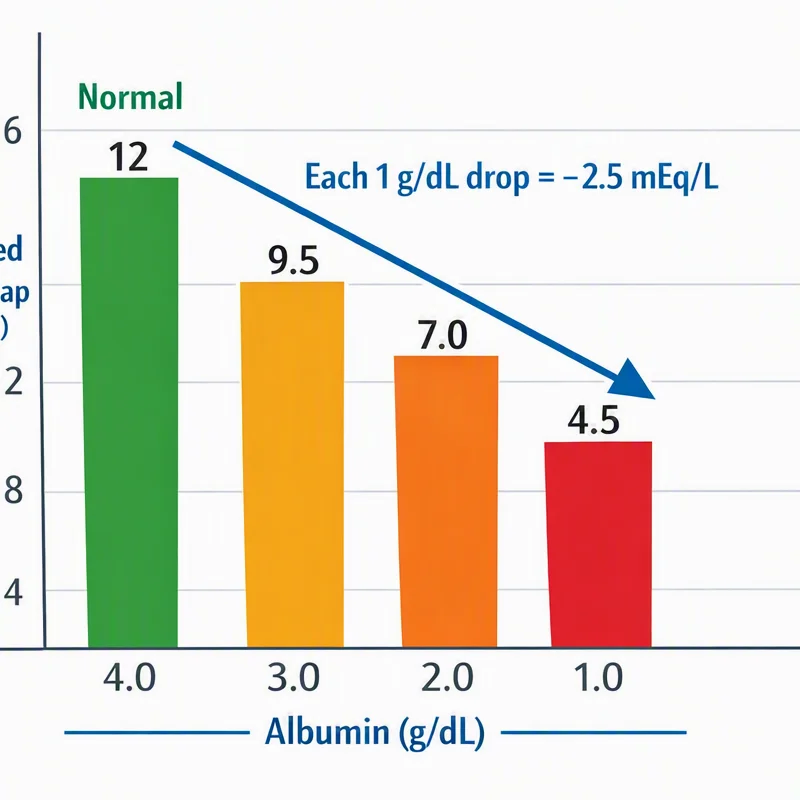
Albumin is especially important because it is a major unmeasured anion. If albumin is low, the anion gap may appear falsely normal. That is why an albumin-corrected anion gap is often more informative than the raw number. This type of gap correction helps improve laboratory interpretation and avoids missing clinically important acidosis.
How Methanol Causes High Anion Gap Metabolic Acidosis
Yes, the direct answer is clear: methanol may lead to a high anion gap In methanol poisoning, methanol itself does not serve as the main acid problem at first. Instead of that, methanol is metabolized into formic acid, which is toxic and drives metabolic acidosis. When formic acid accumulates, the body’s acid-base balance shifts toward systemic acidosis, and the anion gap rises because those acids are not directly measured by routine labs.
That is why methanol is one of the classic toxic alcohols connected with an elevated anion gap. The process begins after toxic ingestion or other exposure, when alcohol dehydrogenase converts methanol into formaldehyde and then to formic acid. Formic acid is the primary factor of the metabolic derangement. As it builds up, it uses up bicarbonate, lowering bicarbonate and producing a high anion gap state.
This biochemical process also explains why symptoms may be delayed. Early after ingestion, the anion gap may not be very high yet, especially if methanol has not been fully metabolized. Later, as more formic acid accumulates, the gap often rises and acidosis becomes more obvious. This progression is important for clinical suspicion and for deciding when to pursue a full diagnostic workup.
Methanol toxicity also causes characteristic end-organ effects. Because formic acid is especially harmful to the optic nerve and retina, patients may develop visual disturbances, blurred vision, or other signs of ocular toxicity. These findings, combined with acid-base abnormalities, create a strong concern for a toxic ingestion that requires emergency attention.
How to Interpret an Anion Gap Calculator Output
An anion gap calculator is valuable, but the result should not ever be read by itself. A “normal” value does not necessarily mean there is no toxic alcohol exposure, and a high value does not prove methanol. The first step is to check the result with the expected range used by the lab and then determine whether the patient has metabolic acidosis as shown by low bicarbonate, low pH, or both.
A normal anion gap suggests there is no obvious accumulation of unmeasured acids at that moment, but it does not rule out early methanol exposure. If the patient presents early after ingestion, serum methanol may still be present before significant formic acid production. In that setting, the osmolar gap may be more useful initially, while the anion gap rises later as metabolism progresses.
Albumin must be considered in any serious interpretation. Low albumin lowers the baseline gap, so a patient with substantial acid load can appear deceptively normal. Using an albumin-corrected anion gap can uncover an abnormality that the uncorrected calculation misses. This is a key point in reliable acid-base interpretation and should be part of every thorough review of serum electrolytes.
There Find more information are also practical nuances:
- An increasing gap over time is often more concerning than a single snapshot. Low bicarbonate with a modest gap may still reflect significant acid-base disease. Mixed disorders can blur the picture, especially in critically ill patients. Clinical context counts more than the calculator alone.
In short, the anion gap calculator is a screening and interpretation tool. It helps detect whether there are unmeasured anions consistent with toxic ingestion, lactic acid production, or another cause of metabolic derangement, but it should be paired with blood gas analysis, osmolality, and bedside assessment.
Typical Test Results in Methanol Toxicity
A number of lab findings frequently appear together in methanol toxicity. One especially important finding is an increased osmolar gap early in the course. This finding reflects the presence of not directly measured osmotically active substances, including methanol itself. As metabolism progresses, the osmolar gap may fall while the anion gap rises, because the parent alcohol is converted into acidic metabolites.
An arterial blood gas is important for assessing severity. It can indicate the degree of acidemia, the respiratory compensation, and whether there is a mixed disorder. In methanol poisoning, blood gas analysis often reveals metabolic acidosis with a low pH and reduced bicarbonate. The pattern may be marked, especially if diagnosis is delayed.
Lactate can be elevated as well, but it should not distract from the main diagnosis. Sometimes a true secondary lactic acidosis develops from tissue hypoxia, shock, or poor perfusion. In other cases, lab artifacts or overlapping illness cloud the picture. Either way, lactate does not confirm or rule out methanol by itself.
Bicarbonate is often low because it is used up buffering the acid load. The drop in bicarbonate is one of the reasons the anion gap rises. In severe cases, serum bicarbonate can be markedly depressed, reflecting major systemic acidosis and the need for urgent treatment.
Other useful findings include:
- Increased serum osmolality or an increased osmolar gap Low pH on blood gas analysis Electrolyte abnormalities that affect acid-base interpretation Signs of end-organ injury, including neurologic symptoms or ocular toxicity
When the laboratory pattern matches, methanol should remain high on the differential, especially if there is concern for toxic ingestion and the patient shows worsening metabolic derangement.
Diagnostic Differential of high anion gap metabolic acidosis
Even though methanol is a classic cause, it is only one part of the broader differential diagnosis of high anion gap metabolic acidosis. Many other conditions can create the same pattern, and close comparison helps avoid diagnostic error. The most common alternatives include lactic acidosis, ketoacidosis, and uremia.
Lactic acidosis is often seen in infection, circulatory collapse, hypoxia, seizures, or severe tissue hypoperfusion. It can produce a high anion gap because lactate is an unmeasured anion. In many patients, it is the primary explanation for metabolic acidosis in the hospital setting.
Ketoacidosis occurs in diabetic ketoacidosis, alcoholic ketoacidosis, and starvation states. Ketone bodies act as unmeasured acids and increase the gap. The clinical context, glucose level, and ketone testing help separate ketoacidosis from toxic alcohol exposure.
Uremia from kidney failure can also produce a high anion gap. When the kidneys cannot clear acid effectively, multiple retained solutes contribute to the gap. Because renal failure can coexist with other illnesses, it may obscure or overlap with toxic ingestion.
Ethylene glycol is another critical toxic alcohol in the differential. It often causes high anion gap metabolic acidosis as well, and the distinction matters because treatment and complications differ. Ethylene glycol may also cause kidney injury and crystal formation, while methanol more strongly raises concern for visual injury.
In practice, the differential diagnosis should be organized by the clinical picture, the osmolar gap, blood gas findings, ketones, kidney function, and exposure history. No single value replaces thoughtful acid-base interpretation.
When Methanol Should Be Suspected
Methanol should be suspected when a patient has an unexplained acid-base disturbance plus a compatible exposure history or clinical pattern. The primary clue is a history of ingestion or possible exposure to contaminated alcohol or industrial products. Because patients may not always give a clear history, the clinician must often rely on secondary findings.
Findings that suggest methanol exposure include visual symptoms such as blurred vision, “snowfield” vision, or loss of sharpness. These findings are especially concerning because they point toward formic acid toxicity and possible ocular injury. The presence of neurologic symptoms such as cephalgia, confusion, ataxia, or deteriorating consciousness also should prompt concern.
Central nervous system depression can occur in advanced toxicity and should be treated as an emergency. A patient may appear intoxicated, but the severity of the acidosis is often disproportionate to a simple ethanol effect. That mismatch is one reason methanol and other toxic alcohols deserve urgent attention.
Other clues include:
- An unexplained high anion gap with low bicarbonate Increased osmolar gap in the right setting Progressive worsening after an apparent delay Possible exposure from a toxic ingestion
Because the presentation can be nonspecific at first, methanol is often a diagnosis of clinical suspicion supported by laboratory evidence. Prompt recognition is key to preventing severe acidosis, vision loss, and organ failure.
Treatment Overview
Management of methanol poisoning is time-sensitive and should begin immediately after the diagnosis is suspected. The primary antidotal treatment is fomepizole, which prevents the action of alcohol dehydrogenase and stops methanol from being converted into formic acid. By stopping this metabolic pathway, fomepizole helps prevent worsening acidosis and toxic metabolite formation.
Hemodialysis may be needed when acidosis is significant, methanol levels are high, visual symptoms are present, or the patient is clinically unstable. Dialysis removes methanol and formic acid directly and also corrects acid-base abnormalities. It is a key intervention in severe poisonings and is often used together with the antidote.
Sodium bicarbonate is frequently used to help improve severe acidosis and support acid-base balance. It does not remove the toxin, but it can temporarily improve pH while definitive therapy is arranged. The decision to give bicarbonate depends on severity, pH, and the full clinical situation.
Supportive care remains essential. This includes airway management if needed, monitoring of electrolytes and blood gas values, treatment of complications, and careful reassessment. Because patients can deteriorate quickly, methanol poisoning is an emergency evaluation scenario rather than a observe-only problem.
Ultimately, treatment aims to halt toxic metabolism, remove the poison, and steady the patient while the diagnostic workup continues.
FAQ: Methanol and Anion Gap
Could methanol lead to a high anion gap?
Yes, it can. Methanol can produce a elevated anion gap because it is broken down into formic acid, which leads to high anion gap metabolic acidosis. The increase in the gap reflects unmeasured acids collecting in the blood as bicarbonate drops.
How does methanol toxicity elevate the anion gap?
Methanol toxicity increases the anion gap because the body turns methanol into formic acid, an acid that is not directly measured on routine chemistry panels. As acid rises, bicarbonate is depleted and the gap rises. This is a textbook example of acid accumulation and systemic acidosis in toxic ingestion.
How does one explain the difference between an anion gap and an osmolar gap?
The anion gap shows unmeasured anions and assists in identify metabolic acidosis. The osmolar gap indicates unmeasured osmoles in the blood and is often raised early in toxic alcohol exposure. In methanol poisoning, the osmolar gap may be elevated first, then the anion gap rises later as methanol is converted to formic acid.
Will a normal anion gap rule out methanol poisoning?
No. A normal anion gap does not rule out methanol poisoning, especially soon after ingestion or when albumin is low. The patient may still have methanol in the blood before enough formic acid has formed. That is why clinicians also rely on osmolar gap, arterial blood gas findings, symptoms, and overall clinical suspicion.
Which lab tests are most useful when methanol ingestion is suspected?
The most useful tests include serum electrolytes, bicarbonate, albumin for gap correction, anion gap calculator output, osmolar gap assessment, arterial blood gas, lactate, serum osmolality, and toxicology-related testing when available. These results aid diagnosis, guide acid-base interpretation, and help distinguish methanol from lactic acidosis, ketoacidosis, ethylene glycol exposure, and other causes of metabolic acidosis.