What is anion gap and how is it calculated?
The anion gap value is a calculated gap used to aid clinicians evaluate acid base balance and find causes of metabolic acidosis. It reflects the difference between routinely measured cations and anions in the blood, which helps reveal the presence of hidden anions. An Anion Gap Calculator is a practical way to estimate this value from standard blood chemistry tests, especially when reviewing an acidotic state.
In most cases, the calculation uses Na, chloride, and bicarbonate level. A common formula is sodium minus the sum of chloride and bicarbonate. Some versions also include serum albumin because low albumin can reduce the measured gap and hide a disorder. That is why anion gap correction matters when albumin is abnormal.
In everyday clinical use, the anion gap helps separate high anion gap metabolic acidosis from normal anion gap metabolic acidosis. A high gap suggests that acids or toxic metabolites are accumulating in the blood, while a normal gap often points to bicarbonate loss or impaired acid excretion without a rise in unmeasured acids.
Because the result comes from a calculation rather than a direct measurement, the value is only as reliable as the rest of the lab assessment. Interpretation should always consider the patient’s symptoms, electrolyte levels, and overall clinical picture.
How does isoniazid affect acid-base balance?
Isoniazid is a core drug in tuberculosis treatment, but at high doses it can cause serious toxicity. Its most important metabolic effect is on the central nervous system and acid-base status. In an overdose scenario, isoniazid can trigger seizures, profound metabolic derangement, and worsening metabolic acidosis.
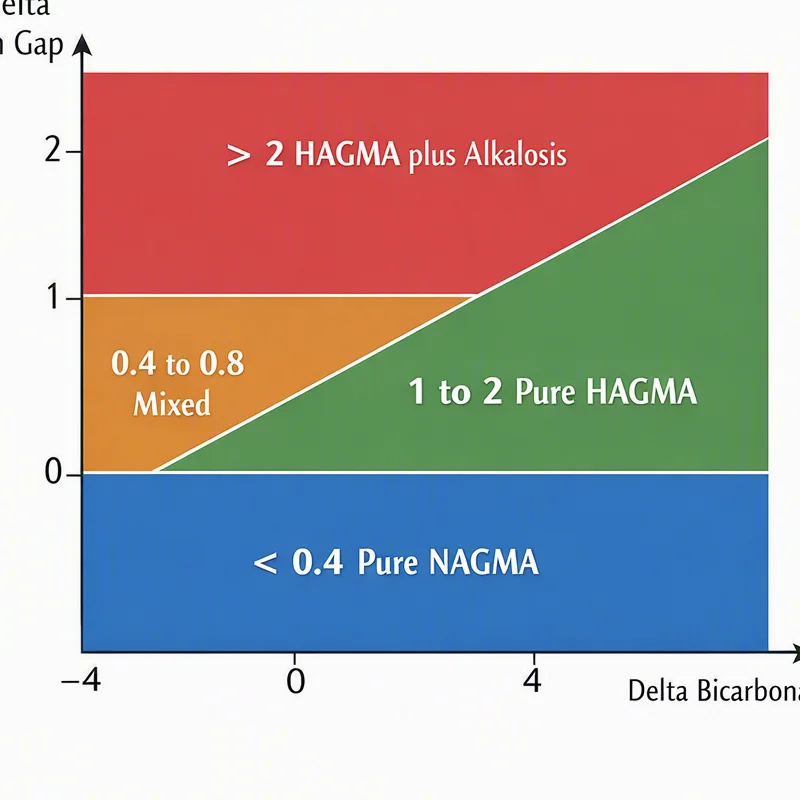
The drug interferes with pyridoxine, also known as vitamin B6, which is crucial for neurotransmitter synthesis and normal neurologic function. Functional vitamin B6 deficiency can develop during toxicity, making the brain more excitable and increasing the risk of seizures and coma. The resulting physiologic stress can contribute to a more acidic state and an abnormal anion gap.
When seizures occur, they may boost anaerobic metabolism and drive lactic acidosis. This is a major reason isoniazid toxicity can cause an acidotic state rapidly. Severe cases may also involve hypotension, poor tissue perfusion, and respiratory compromise, all of which can worsen acidosis.
From an acid-base standpoint, the key issue is not only the medication itself, but the cascade it can produce: neurologic toxicity, impaired respiration, and excess lactate. That is why blood gas analysis is often important when isoniazid exposure is suspected.
Can isoniazid cause high anion gap metabolic acidosis?
Indeed. Isoniazid can cause high anion gap metabolic acidosis, especially in substantial drug overdose or severe toxicology scenarios. The main mechanism is usually indirect: convulsions and cellular hypoxia can raise lactate, leading to a higher calculated gap.
It does not mean every person taking isoniazid will develop a high anion gap. Therapeutic use for tuberculosis treatment is generally safe when properly monitored. The concern arises when there is excessive ingestion, poor clearance, or a mixed toxin-induced picture. In that setting, the anion gap becomes a helpful marker of metabolic burden.
There are also important alternative explanations for a high gap that must be considered. For example, pyroglutamic acid build-up can occur in some drug-related or nutritional states and is another source of high anion gap metabolic acidosis. Clinically, however, isoniazid toxicity is more classically associated with lactate-driven acidosis rather than pyroglutamic acid.
It is also worth separating this from normal anion gap metabolic acidosis, which has a different differential diagnosis. If the gap is not elevated, the clinician should not focus solely on isoniazid alone; other acid-base disorders may be present, or the measured values may reflect timing, treatment, or concurrent conditions.
In short, isoniazid can certainly be part of a high-gap picture, but the gap itself is a hint, not the diagnosis. The clinical suspicion must be based on exposure history, symptoms, and a full diagnostic workup.
What symptoms and lab findings may appear?
Clinical presentation may range from mild neurologic symptoms to a serious emergency. Early symptoms may include nausea, vomiting, dizziness, and agitation. As toxicity progresses, altered mental status, fits, and coma can develop. Breathing effort may rise, leading to tachypnea as the body tries to compensate for the acidosis.
In laboratory testing, clinicians often look for metabolic acidosis in blood gas testing, with reduced pH and bicarbonate levels. The serum bicarbonate may be markedly decreased, and the electrolyte profile may show an elevated anion gap. A measured lactate can support the suspicion of lactic acidosis.
Other findings may include abnormal serum chemistries, changes in potassium, and possible signs of organ stress from prolonged seizures or poor perfusion. Since acidosis affects ventilation, respiratory compensation may be present, often seen as a low carbon dioxide level on blood gas testing.
If neurologic symptoms and unexplained metabolic acidosis are present together, concern for a toxin-related process should be raised and immediate evaluation should follow.
In practice, the Anion Gap anion gap in chronic kidney disease Calculator can help quickly confirm whether the pattern is high gap or not, though it should never replace bedside assessment. The presence of strong suspicion is what guides the next steps.
How is isoniazid toxicity recognized and addressed?
Diagnosis starts with a detailed history, because prompt recognition can be critical. If there is any suspicion of accidental or intentional drug overdose, the clinician should consider a toxic exposure until shown otherwise. The diagnostic workup typically includes blood gas analysis, glucose testing, electrolytes, renal function, lactate, and toxicology screening when HAGMA explanation appropriate.
The antidote for isoniazid toxicity is pyridoxine. It helps correct the functional vitamin B6 deficiency induced by the overdose and is central to emergency treatment. In severe cases, repeated or large doses may be needed based on the estimated ingestion amount and clinical response.
Depending on timing and the patient’s condition, activated charcoal may be given if the ingestion was recent and the airway is protected. However, the priority is stabilizing and supporting the patient, stopping seizures, and correcting acidosis. This is where supportive care becomes vital.
Supportive management may include oxygen, IV fluids, seizure control, and monitoring in a high-acuity setting. If the patient cannot protect the airway, has ongoing seizures, or is profoundly altered, intubation may be necessary. These measures address the immediate consequences while pyridoxine works on the underlying toxicity.
Because isoniazid toxicity can progress rapidly, early recognition and emergency treatment are essential. The clinical goal is to control seizures, improve perfusion, and correct the acidotic state before organ injury progresses.
When should high anion gap be worked up more?
A high gap should consistently trigger a stepwise evaluation rather than a single cause assumption. The range of causes is broad and includes renal failure, ketoacidosis, sepsis, salicylates, methanol, and other poisoning-related causes. In many cases, more than one process is present at the same time.
Renal failure can impair acid clearance and allow unmeasured acids to accumulate. Ketoacidosis, whether diabetic, alcoholic, or starvation-related, is a frequent cause of high anion gap metabolic acidosis. Sepsis may lead to lactic acidosis from poor perfusion and inflammatory stress. Methanol ingestion is particularly important because it can produce severe toxicity and vision-threatening complications.
Medication exposures should also be checked carefully. Salicylates can produce a mixed acid-base disorder, and toxic ingestion histories often overlap. If isoniazid is part of the history, clinicians should think in terms of the broader toxicology picture rather than assuming the elevated gap confirms one diagnosis.
The decision to investigate further depends on the degree of abnormality, symptoms, and the presence of additional clues such as altered mental status, hypotension, or worsening neurologic symptoms. A high gap that is unexplained after the first pass of testing requires a more detailed diagnostic workup, including repeat electrolytes, repeat blood gas analysis, lactate, ketones, kidney studies, and targeted toxicology testing.
The main point is that a high anion gap is a indicator of underlying metabolic derangement. It is not the final answer. When the pattern is marked or unexplained, urgent evaluation is warranted.
FAQ about isoniazid and anion gap
Can isoniazid cause a high anion gap?
Yes. Isoniazid can lead to high anion gap metabolic acidosis, especially in an overdose setting. The rise is often driven by seizures, tissue hypoxia, and lactic acidosis rather than a direct isolated effect on the anion gap.
Which acidosis is seen with isoniazid toxicity?
The typical finding is metabolic acidosis, often with a high anion gap. Severe toxicity may also trigger lactic acidosis after seizures or poor perfusion, which makes the acid-base disturbance more pronounced.
What is pyridoxine’s role in isoniazid overdose?
Pyridoxine is the antidote for isoniazid toxicity. It replaces the depleted functional vitamin B6 and helps stop seizures, which can reduce worsening acidosis and improve the patient’s clinical state.
What labs are checked when the anion gap is high?
Common labs include electrolytes, serum bicarbonate, blood gas analysis, lactate, kidney function tests, glucose, and toxicology studies when indicated. Albumin should also be checked because it affects interpretation of the anion gap.
When is a high anion gap a medical emergency?
A high anion gap is a medical emergency when it is accompanied by confusion, seizures, coma, hypotension, or suspected toxic ingestion. In those cases, immediate clinical evaluation is needed because the cause may be a life-threatening acid-base disorder.