An anion gap calculator is more informative than a simple calculator when you need quick, accurate diagnostic interpretation of serum electrolytes. In practice, the anion gap helps clinicians assess acid-base balance, screen for metabolic acidosis, and narrow a broad differential diagnosis by identifying likely causes of unmeasured anions from disorders driven by clear bicarbonate loss or chloride retention. When used properly, it becomes part of a broader diagnostic algorithm rather than a stand-alone result.
This guide covers how the anion gap formula works, how to interpret a normal anion gap versus an elevated anion gap, and how to adjust for hypoalbuminemia using albumin correction. It also demonstrates how to connect the result to real-world causes such as lactic acidosis, ketoacidosis, renal failure, renal tubular acidosis, and toxic alcohol ingestion.
What the Anion Gap Measures
The anion gap is a derived value derived from common electrolytes on a basic metabolic panel. It estimates the difference between measured positively charged ions and measured negatively charged ions, aiding clinicians infer the presence of unmeasured anions in the blood. Because the body maintains tight acid-base balance through buffer systems and kidney function, changes in the gap can signal a significant metabolic derangement.
In the classic interpretation, sodium is compared against chloride and bicarbonate, which are the main contributors in routine chemistry testing. The gap represents the balance between these measured ions and other charged particles not directly reported, such as proteins, phosphate, sulfate, lactate, and organic acids. This is why the gap can reveal a hidden acid-base disorder even before the precise cause is known.
The test is often used as part of clinical assessment when a patient presents with low bicarbonate, altered mental status, https://anion-gap-test287.lumenforgex.com/posts/how-the-anion-gap unexplained tachypnea, or an abnormal metabolic profile. A single number does not confirm the diagnosis, but it can quickly guide attention toward the right branch of the differential diagnosis.
Anion Gap Calculation and Calculation Inputs
The usual formula for anion gap is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians include potassium in the formula, especially in older references or specific methods:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Most modern clinical use prioritizes the sodium-based version because potassium is usually low in relation to sodium and adds limited value to routine interpretation. Still, an anion gap calculator may use either approach, so it is important to know which formula is being applied. Subtle changes in the equation can shift the number enough to affect clinical decision-making.
The main inputs are drawn from the electrolyte panel or chemistry panel: sodium, chloride, and bicarbonate. In many cases, the calculator also asks for albumin because low protein levels can mask a clinically important elevation. Since serum albumin level strongly influences the baseline gap, a raw number without context can be misleading.
As an example, a patient with sodium 140, chloride 104, and bicarbonate 24 has an anion gap of 12. That value may be normal depending on the lab’s reference range, but the interpretation changes if the patient has severe hypoalbuminemia or evidence of metabolic acidosis. The calculation is only the starting point for clinical interpretation.
Interpreting a Within-Range vs Elevated Anion Gap
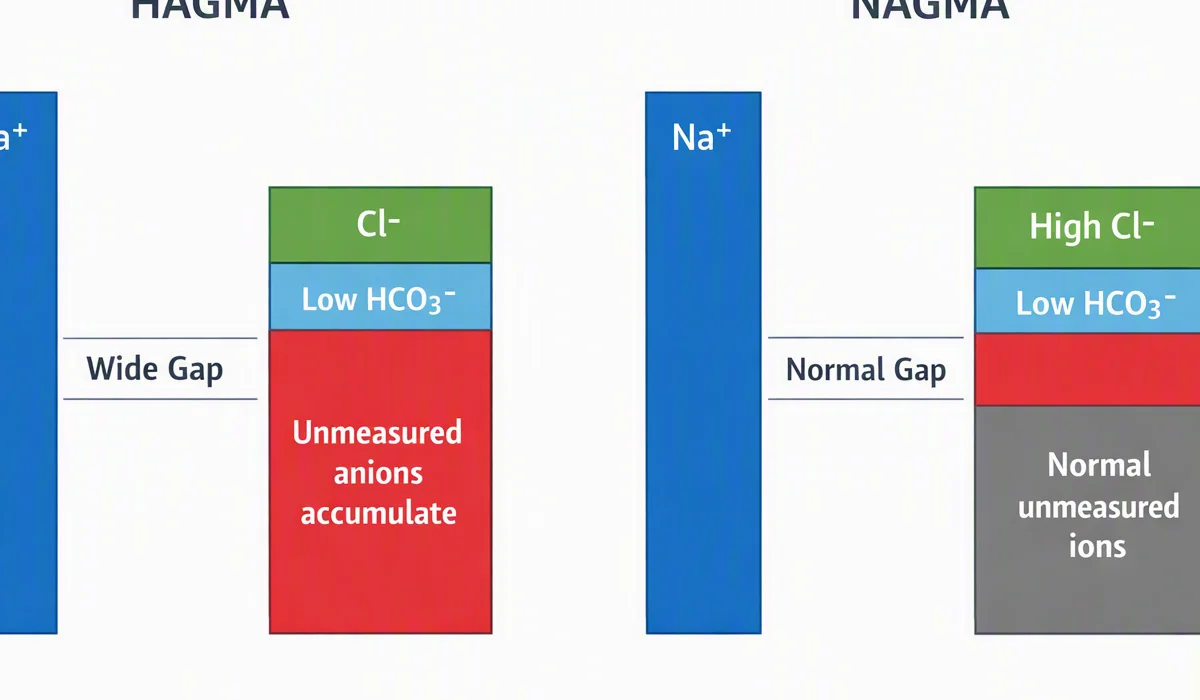
Assessment starts from the lab’s reference range, since typical readings vary slightly by assay and institution. In general, a normal anion gap suggests that the bicarbonate decrease is being balanced by a rise in chloride, while an elevated anion gap indicates accumulation of unmeasured acids or their anions. Both findings can indicate metabolic acidosis, but they point to different etiologies.
A high anion gap metabolic acidosis usually means acid is being added to the body or retained because the kidneys cannot clear it effectively. Common causes include organic acids and toxins. By contrast, a normal anion gap metabolic acidosis is often a hyperchloremic process, where bicarbonate is lost and chloride rises to maintain electroneutrality.
Practical interpretation works best as a branching diagnostic algorithm:
- Normal anion gap: think bicarbonate loss or renal acid-handling problems. Elevated anion gap: think added acids, accumulation of acids, or toxin exposure. If the number seems unexpectedly normal, check albumin and consider anion gap correction.
It is equally important to confirm whether the patient actually has metabolic acidosis. A reduced bicarbonate value on a chemistry panel is not sufficient on its own; an arterial blood gas can clarify pH and respiratory compensation. This is particularly helpful when mixed acid-base disorders are possible.
Corrected Anion Gap for Hypoalbuminemia
Albumin is a key not directly measured anion, so reduced albumin decreases the measured anion gap. That means a patient with hypoalbuminemia may have a misleadingly regular or only slightly elevated result despite meaningful acidosis. This is why albumin correction is important in standard interpretation.
The corrected anion gap adjusts the measured value upward when serum albumin is below normal. Several correction methods are available, but a common clinical approach is to add a fixed amount for each gram per deciliter albumin is below normal. The exact factor may vary by institution, so the calculator should be used in line with local practice or its stated assumptions.
This anion gap correction is especially valuable in critically ill patients, patients with malnutrition, liver disease, chronic inflammation, or nephrotic states. In these settings, the raw number may diminish the burden of unmeasured anions and therefore mask a true acid-base disorder.
Consider this clinical logic: a patient has low bicarbonate and a “normal” gap, but the serum albumin level is markedly reduced. After albumin correction, the gap becomes elevated, revealing a mixed picture or a hidden high-gap process. In other words, the corrected number can change the differential diagnosis and the priority of workup.
Diagnostic Approach of High Anion Gap Metabolic Acidosis
high anion gap metabolic acidosis happens when acids build up or are not cleared. In essence, bicarbonate is consumed while the resulting anions are not captured in the standard panel. The result is a broadened gap and a focused differential.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one has typical clinical clues, but duplication is frequent, so the anion gap should be combined with medical history, exam, and lab values.
- Lactic acidosis: frequently linked to hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Ketoacidosis: encompasses starvation ketosis, alcoholic ketosis, and diabetic ketoacidosis, which often presents with hyperglycemia, dehydration, and ketones. Renal failure: decreased acid excretion leads to build-up of acids and progressive metabolic derangement. Toxic alcohol ingestion: such as methanol or ethylene glycol, which can produce severe high-gap acidosis and end-organ injury.
In diabetic ketoacidosis, the gap is often greatly elevated because ketone bodies pile up. In kidney failure, the pattern may change with progressive retained acids and a decline in renal clearance. With toxic alcohol ingestion, the anion gap can climb early, and the clinical picture may include osmolar gap alterations, visual symptoms, neurologic decline, or kidney injury depending on the agent.
By using an anion gap calculator here helps prioritize the next step in clinical assessment: lactate testing, ketone testing, toxicology testing, or renal function review. The value doesn’t replace clinical judgment, but it sharpens the diagnostic differential.
Differential Diagnosis of normal anion gap metabolic acidosis
A normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. Here, the issue is usually not the addition of unmeasured acid, but rather alkali loss or impaired renal acid handling. The anion gap remains normal because chloride substitutes for the lost bicarbonate.
Key causes include diarrhea and renal tubular acidosis. Gastrointestinal bicarbonate loss is a classic mechanism in diarrhea, especially when losses are prolonged or severe. The kidneys may also fail to acidify urine properly in renal tubular acidosis, producing a chronic or recurrent normal-gap acidosis.
Other contributors to normal anion gap metabolic acidosis can include high-volume saline administration, certain medications, and tubular dysfunction, but the main clinical distinction remains the same: chloride increases as bicarbonate falls. This explains why the serum chemistry pattern matters as much as the calculated number.
If you see a normal-gap pattern, ask whether the problem is a true loss of alkali. If the answer is yes, then bicarbonate loss from the gut or kidney becomes central to the diagnostic workup. That makes the anion gap an efficient tool for directing the next branch of the acid-base differential diagnosis.
Typical Calculation Errors and Clinical Setting
Even when a accurate calculation can mislead if the clinical context is overlooked. One common issue is lab error, such as specimen contamination, recording error, or a discordant set of results. Before deciding that a severe acid base problem is occurring, check that the lab values are self-consistent and compatible with the patient’s symptoms.
Another pitfall is overlooking albumin. If the protein concentration is low, the raw anion gap may downplay the true burden of unmeasured anions. For this reason albumin correction should be taken into account in any patient with suspected metabolic acidosis and low albumin.
The delta gap is an additional important concept. When the anion gap is high, the delta gap compares the rise in the gap to the fall in bicarbonate. This helps detect mixed acid-base disorders, such as coexisting metabolic alkalosis or an additional normal-gap acidosis. In practice, the delta gap can indicate whether the patient’s metabolic profile is more intricate than the first calculation suggests.
Additional common pitfalls include using the wrong reference range, failing to verify pH on an arterial blood gas, and interpreting a single number without considering respiratory compensation. The most reliable results come from combining the calculator output with a full clinical assessment and the broader picture of electrolyte imbalance and organ function.
When to Use an Anion Gap Calculator in Clinical Workflow
An anion gap calculator is most useful early in the evaluation of suspected acid-base disorder. It fits naturally into a workflow that begins with a basic metabolic panel or electrolyte panel, then moves to an arterial blood gas when pH and compensation need clarification. This sequence promotes efficient clinical decision support and more focused testing.
Use the calculator for low bicarbonate levels, when there is unexplained tachypnea or altered mental status, or when toxin exposure is suspected, sepsis, renal dysfunction, or ketoacidosis. It is also useful when following repeated laboratory results because changes in the anion gap can monitor improvement or progression in the underlying metabolic derangement.
In practical terms, the workflow often looks like this:
- Check the basic metabolic panel for sodium, chloride, and bicarbonate. Perform the anion gap calculation using the calculator. Measure albumin and apply corrected anion gap logic if needed. Order an arterial blood gas to confirm acidemia or alkalemia and assess compensation. Move to the appropriate differential diagnosis for high-gap or normal-gap causes.
This approach makes the calculator part of a more comprehensive clinical decision-making process rather than a standalone number generator. It helps clinicians advance efficiently from a chemistry abnormality to a meaningful explanation, especially in urgent settings.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the difference between measured cations and anions on a chemistry panel. Clinically, it helps identify metabolic acidosis, inform acid-base differential diagnosis, and distinguish between high-gap and normal-gap causes of acid-base disorders. It is especially helpful when combined with albumin and arterial blood gas data.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some methods also add potassium, but the sodium-based formula is most commonly used. The values usually come from a basic metabolic panel or related electrolyte panel.
Why does low albumin affect the anion gap?
Albumin is a primary unmeasured anion, so when hypoalbuminemia is present, the measured gap can appear lower than it truly is. For that reason albumin correction is important. A corrected anion gap more accurately reflects the real burden of unmeasured acids and improves diagnostic interpretation.

What leads to a high anion gap metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions elevate unmeasured acids or reduce acid clearance, increasing the gap and indicating a significant metabolic problem.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A patient can have normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern often occurs with diarrhea or renal tubular acidosis, where bicarbonate loss is matched by a rise in chloride. In that setting, the gap stays normal even though true acidosis is present.