What Is the Anion Gap?
This anion gap is a derived value that helps clinicians assess acid-base balance by comparing the major measured cations and anions in the blood. It is most often derived from routine serum electrolytes, especially sodium, chloride, and bicarbonate. As the body maintains electrical neutrality, the anion gap estimates the difference between measured positively charged and negatively charged particles, indirectly Click here for info reflecting unmeasured ions.
In clinical practice, the anion gap is especially useful when evaluating metabolic acidosis. A shift in the gap often points toward excess acids, lost bicarbonate, or laboratory patterns that require a broader diagnostic approach. As it uses routine lab data, it is one of the simplest tools for detecting an acid-base disorder and refining the differential diagnosis.
Even though the exact number can vary based on the lab’s reference range, a normal result usually suggests that measured cations and anions are in expected balance. A higher-than-expected result can indicate high anion gap acidosis, while a normal value in the setting of acidosis may indicate normal anion gap or hyperchloremic processes. That distinction is central to clinical interpretation.
How the Anion Gap Calculator Works
An anion gap calculator simplifies the anion gap formula so that clinicians can quickly interpret laboratory values and assess for an electrolyte imbalance. The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions include potassium, but most bedside interpretation relies on the streamlined formula above. The calculator uses serum sodium, serum chloride, and serum bicarbonate to determine the amount of unmeasured anions in the plasma. A wider gap usually suggests build-up of organic acids or other unmeasured substances.
The calculator becomes even more helpful when albumin is abnormal. Because albumin is a negatively charged protein and a major unmeasured anion, low albumin can make the gap appear falsely normal. That is why many clinicians apply albumin correction before final interpretation. The output is often a corrected anion gap, which gives a more accurate picture of the patient’s underlying acid-base status.
In real-world use, the calculator supports rapid blood gas analysis and complements the exam of acid-base patterns. It does not replace clinical judgment, but it streamlines the first step in recognizing metabolic acidosis, especially when the cause is not immediately obvious.
Why the Anion Gap Matters in Acid-Base Balance
Anion gap is useful because it helps separate different categories of acid-base balance issues. When metabolic acidosis is present, the gap can suggest either a high anion gap or a normal anion gap picture. This separation is significant because the causes, urgency, and treatment strategies are often different.
In high gap acidosis, the body has built up unmeasured acids. In normal gap acidosis, bicarbonate is often lost and replaced by chloride, which maintains the gap but still produces acidemia. This is why the anion gap is not just a number; it is a tool for understanding the underlying buffering system and how the body reacts to an acid-base disorder.
It also can reveal a mixed disorder. For example, a patient may have a metabolic acidosis and a second process affecting pH, such as respiratory compensation that is inadequate or exaggerated. In these cases, the anion gap adds clarity to the clinical interpretation of the patient’s labs and symptoms.
Because the gap is tied to measured and unmeasured ions, it is a helpful connection between routine chemistry testing and deeper physiologic reasoning. That makes it a essential tool in both routine medicine and urgent evaluation.
How to Interpret a Elevated Anion Gap
A high anion gap usually means that unmeasured acids are present in greater amounts. This is a classic finding in various important causes of metabolic acidosis, and it should prompt a focused search for the origin of the acid load.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. In lactic acidosis, tissue poor perfusion, sepsis, seizures, or major physiologic stress can raise lactate production. In ketoacidosis, ketone bodies build up when insulin is too low or when starvation and alcohol-related states change metabolism. Renal failure can reduce acid excretion, allowing unmeasured acids to build up. Toxic alcohol ingestion is another major cause because substances such as methanol or ethylene glycol generate acid metabolites that increase the gap.
When the gap is high, the next question is not just “Is it high?” but “Why is it high?” That requires combining the anion gap with the patient’s history, exam, and other lab data. A patient with acidemia, elevated lactate, and hypotension may have lactic acidosis. Someone with hyperglycemia or starvation may point toward ketoacidosis. Kidney function tests, osmolar calculations, and toxicology clues may be needed in other scenarios.
A high gap is especially concerning because it can signal a critical condition that needs rapid treatment. The anion gap calculator helps identify the pattern early, but the clinician must then link it to the patient’s overall presentation.
How to Understand a Normal Anion Gap
A normal anion gap doesn't eliminate metabolic acidosis. Rather it typically indicates bicarbonate loss with a compensatory increase in chloride, causing chloride-related acidosis. This is often called normal-anion-gap acidosis.
A very common cause is gastrointestinal fluid loss, where the body sheds bicarbonate-rich intestinal fluid. Another key cause is tubular kidney acidosis, in which the kidneys cannot manage acid or bicarbonate normally. In either case, the bicarbonate loss is central, but the anion gap remains in the expected range because chloride rises to preserve electroneutrality.
This pattern can be easy to overlook if attention is placed only on the pH. A patient may be acidemic with low bicarbonate but still have a normal gap. This is why, a full review of serum electrolytes matters. The serum chloride level often goes up relative to bicarbonate, forming the lab pattern that supports a normal-gap process.
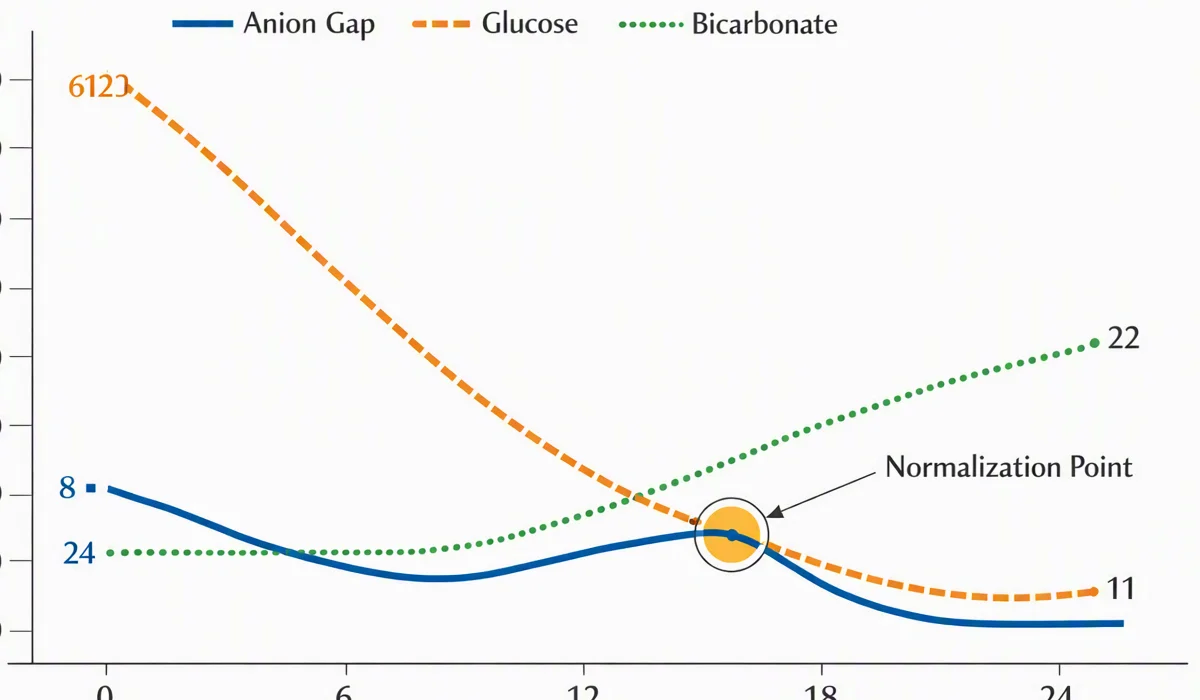
Normal-gap patterns are also important when evaluating treatment effects. For example, after a high-gap acidosis begins to resolve, the gap may normalize while bicarbonate remains low, or the patient may develop a mixed picture. Careful tracking prevents misclassification and supports better medical interpretation.
Serum albumin Recalibration and Additional Important Corrections
Albumin is among the most important elements to evaluate when interpreting the anion gap. Since albumin makes up a large part to the pool of unmeasured anions, hypoalbuminemia can lower the measured gap and mask a clinically significant acidosis. In these cases, albumin correction is crucial.
The resulting corrected anion gap better reflects the true acid burden. Without this adjustment, a patient may look to have a normal anion gap in chronic kidney disease gap even when a high-gap process is present. This is especially important in ill patients with inflammation, malnutrition, liver disease, or critical illness, where low serum albumin is frequent.
Albumin’s role is tied to protein binding and the overall charge balance in plasma. When albumin falls, the baseline anion gap falls too. That means the lab result has to be interpreted in context rather than as an isolated number. A clinician using an anion gap calculator should therefore check whether the tool includes an albumin adjustment or whether correction must be done separately.
Other adjustments may also matter depending on the setting, but albumin is the major one in routine practice. It is a reminder that not all “normal” results are truly normal. If the patient has hypoalbuminemia, a corrected value may reveal hidden high gap acidosis that changes the differential diagnosis and treatment priorities.
Stepwise: How to Determine Acid-Base Equilibrium
A useful method begins with the complete data set: serum electrolytes, an arterial blood gas, and the patient's clinical presentation. The goal is to determine whether there is acidemia or alkalemia, whether the problem is metabolic or respiratory, and whether the anion gap helps explain the pattern.
Initially, review the pH on the blood gas. If the pH is low, acidemia is present. Next, examine bicarbonate and carbon dioxide to decide whether the primary problem is metabolic or respiratory. If bicarbonate is low, metabolic acidosis is likely. At that point, calculate or review the anion gap using sodium, chloride, and bicarbonate.
Second, assess whether respiratory compensation is appropriate. The lungs often reduce carbon dioxide in response to metabolic acidosis. If compensation is not as expected, another process may be present. This is where blood gas analysis and the electrolyte panel should be interpreted together rather than separately.
Then, decide whether the pattern is high-gap or normal-gap. A high-gap pattern should trigger evaluation for lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure. A normal-gap pattern should raise suspicion for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
Lastly, review whether albumin is low and whether a corrected anion gap is needed. This step improves accuracy and can reveal a mixed disorder that would otherwise be overlooked. In short, the process is: assess pH, identify the primary disorder, calculate the gap, correct for albumin, and then interpret the result in context.
Frequent Errors in Anion Gap Analysis
One of the most common oversights is missing lab error or specimen issues. A single abnormal result should always be reviewed against the rest of the panel and the clinical context. If the numbers do not make physiologic sense, repeat testing may be necessary before drawing conclusions.
Another frequent error is disregarding the reference range used by the laboratory. Some analyzers and institutions may have somewhat different normal ranges, so the same numeric result can be interpreted differently depending on the setting. That is why the anion gap should never be treated as a standalone diagnosis.
It is also easy to miss a mixed acid-base disorder. For instance, a patient may have a high anion gap and a separate metabolic alkalosis, or a normal gap with a respiratory process superimposed. The delta gap is helpful here because it compares the change in the anion gap to the change in bicarbonate and can suggest whether additional processes are present.
Another common pitfall is forgetting that low albumin changes the baseline. If hypoalbuminemia is present, the measured anion gap may underestimate the severity of the disturbance. Careful albumin correction lowers this risk and improves diagnostic accuracy.
When You Should Use an Anion Gap Calculator
An anion gap calculator is particularly useful when a prompt, accurate interpretation is needed for clinical decision making. It is particularly valuable during emergency evaluation when a patient presents with vomiting, altered mental status, shock, dyspnea, or signs of acidemia. In these situations, rapid recognition of an acid-base disorder can influence immediate care.
The calculator is also important in critical care, where serial labs are reviewed repeatedly and subtle changes can matter. Patients with sepsis, kidney dysfunction, diabetes, intoxication, or gastrointestinal losses often have changing electrolyte patterns. A calculator helps structure those values into a practical interpretation.
In everyday clinical use, the tool promotes a more structured approach to any suspected acid-base disorder. It can help separate metabolic acidosis from other problems, recognize when albumin correction is needed, and guide next-step testing. Because it links electrolytes, albumin, and the broader clinical picture, it is more than a math aid; it is part of the diagnostic workflow.
To get the best results, use it alongside the patient’s symptoms, medications, kidney function, glucose, lactate, ketones, and blood gas results. That broader context turns a number into practical guidance.
Frequently Asked Questions About Anion Gap and Acid-Base Balance
What is the anion gap and why is it important?
The anion gap is a derived value from sodium, chloride, and bicarbonate that helps measure acid-base balance. It is important because it helps identify metabolic acidosis and distinguish between high anion gap and normal anion gap patterns, which have varying causes and treatment priorities.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). An Anion Gap Calculator performs this calculation instantly using serum electrolytes. If albumin is low, albumin correction may be needed for a more precise result.
What does a high anion gap mean in acid-base balance?
A high anion gap usually means there are additional unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It often signals a clinically important form of metabolic acidosis that needs prompt evaluation.
How does low albumin affect the anion gap?
Hypoalbuminemia reduces the measured anion gap because albumin is a primary unmeasured anion. That can make a true high-gap process look normal. Using a corrected anion gap helps compensate for this effect and supports clinical interpretation.
Can a normal anion gap still occur with metabolic acidosis?
Certainly. A normal anion gap can still be seen with metabolic acidosis, especially when there is bicarbonate loss replaced by chloride. Common causes include diarrhea and renal tubular acidosis, often described as hyperchloremic acidosis or normal gap acidosis.