The gap between ions is a practical way to look at the balance of blood electrolytes in the blood and to help identify certain types of acid-base problems. In chronic kidney disease, it can give important clues about acidosis caused by metabolism, acid-base status, and how well the kidneys are handling acid and waste products. A simple blood test or an Anion Gap Calculator can help clinicians determine whether the pattern of blood chemistry suggests a buildup of extra anions, a different cause of acidosis, or a result that needs further expert review.
Although the concept can sound technical, the basic idea is straightforward: the body’s major charged particles should stay in balance. When that balance shifts, the anion gap can go up, decrease, or stay normal depending on the cause. In chronic kidney disease, those changes may indicate renal dysfunction, retention of acids, or other processes affecting blood chemistry.
What exactly the Anion Gap Measures
The anion gap is a calculated value that measures the difference between the main positive and negative substances in the blood. It is commonly calculated from an electrolyte panel or broader blood chemistry testing. The most common elements are sodium, chloride, and bicarbonate, with potassium occasionally included depending on the formula used.
In practical terms, the anion gap helps gauge the amount of unmeasured anions in the bloodstream. These are negatively charged substances that are not directly reported on a standard lab test but still influence acid-base status. Examples include proteins, phosphates, sulfates, and certain acids that can collect during illness. Because the calculation is indirect, it is best understood as a diagnostic marker rather than a diagnosis by itself.
The classic anion gap calculation is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium, which slightly changes the result. That is one reason an Anion Gap Calculator can be helpful: it uses the chosen formula consistently and reduces arithmetic errors when reviewing lab values.
For most people, the anion gap is a guide to the body’s electrolyte imbalance and overall acid-base balance. When the gap increases, it often suggests that extra acids or acid-related substances are present. When it decreases, the issue may involve low proteins, measurement differences, or less commonly unusual blood chemistry patterns.
How come the Anion Gap Can Change in Chronic Kidney Disease
Chronic kidney disease affects how the kidneys remove waste and balance acids. As kidney function declines, the body may have trouble removing acid and maintaining normal acid-base balance. This can lead to metabolic acidosis, especially when the kidneys can no longer remove enough acid or produce enough bicarbonate to match daily acid production.
One important concept is acid retention. Healthy kidneys remove acid byproducts of metabolism. With renal impairment, those byproducts can accumulate. Over time, this raises the likelihood of a higher anion gap because more unmeasured anions are present in the blood.
That said, chronic kidney disease does not always produce the same acid pattern. Some people develop high anion gap metabolic acidosis, while others have normal anion gap metabolic acidosis. The difference is influenced by how advanced the kidney disease is, how much acid has accumulated, whether bicarbonate is being lost through other pathways, and whether another problem is contributing to the disturbance.
In earlier stages of CKD, a normal anion gap pattern may appear if the body is losing bicarbonate without yet accumulating large amounts of unmeasured acids. In more advanced disease, uremia and retained metabolic waste can push the anion gap upward. This is why clinicians look at the full set of blood test results rather than relying on one number alone.
Typical, Decreased, and High Anion Gap Values
The reference range for the anion gap can vary by facility because multiple analyzers and formulas are used. In many settings, the usual range is roughly within the lower teens, but the exact cutoff should always be considered using the lab’s own benchmark. A result outside the expected range does not automatically mean disease; it indicates the value needs context.
A elevated anion gap usually means that extra acids or acid-related substances are present in the blood. Common causes include metabolic acidosis from kidney failure, lactic acid buildup, ketoacidosis, or toxin exposure. In CKD, a rising gap often reflects progressive acidic waste and declining ability to clear it.
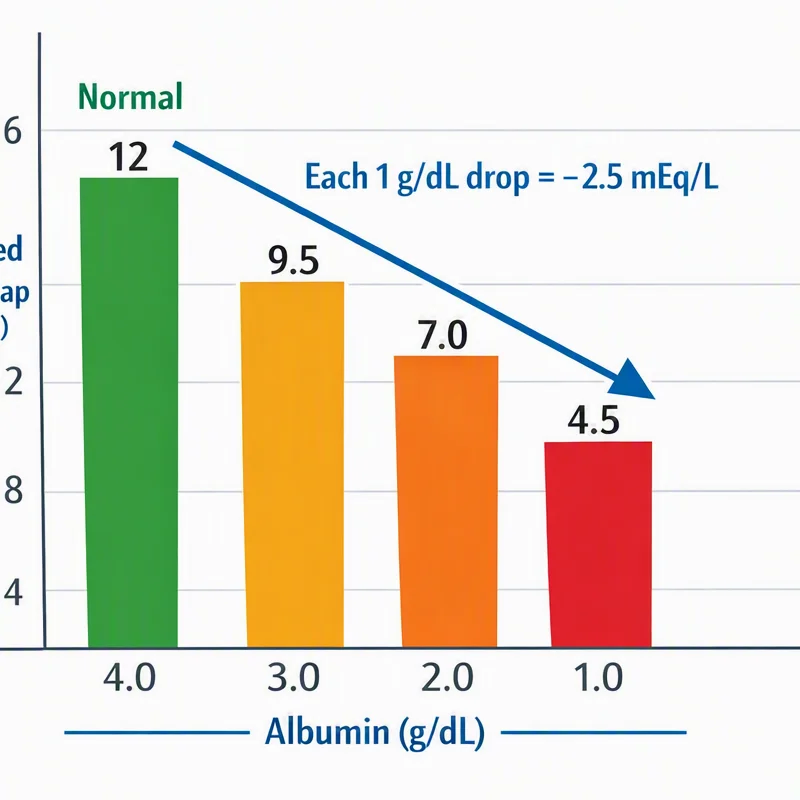
A decreased anion gap is less common. It may be seen with low blood albumin, lab variation, or certain unusual conditions affecting blood proteins or measurement. Because albumin carries negative charge, low albumin can reduce the apparent gap even when acid-base issues are present. This is why hypoalbuminemia matters so much in interpretation.
It helps to think of the anion gap as a indicator, not a verdict. A value that looks normal may still hide an acid-base problem if albumin is low. A value that looks high may reflect true accumulation of acid, but the cause still needs to be determined. That is where careful medical interpretation becomes essential.
In what way an Anion Gap Calculator Is Applied
An Anion Gap Calculator serves as a practical resource for rapidly performing the anion gap calculation from existing lab values. It generally uses sodium, chloride, and bicarbonate, and some calculators also allow potassium to be included. The calculator can be especially helpful when reviewing an electrolyte panel or interpreting intricate serum chemistry results.
Using the calculator is straightforward:
- Input the measured sodium value. Enter the chloride value. Type in the bicarbonate value. Include potassium if the formula being used uses it. Compare the result against the lab’s reference range.
In real clinical work, the calculator is not used in isolation. It is part of a wider review of the acid-base disorder, the patient’s symptoms, and other markers of kidney and metabolic health. For example, a low bicarbonate level with a high anion gap might suggest one type of metabolic acidosis, while low bicarbonate with a normal gap may point to a different process.
The calculator also supports reliability. Different formulas and slight measurement differences can affect the result, so a tool that clearly shows the inputs can improve the reliability of the initial screen. Still, the number itself is only the beginning of interpretation. The surrounding context, including kidney dysfunction and overall blood chemistry, determines what the result means.
Frequent Causes of Elevated Anion Gap in CKD
In chronic renal disease, an increased anion gap often indicates uremia, the buildup of waste products that healthy kidneys would normally remove. These retained substances add to the pool of unmeasured anions, contributing to high anion gap metabolic acidosis. As renal failure progresses, acid handling becomes less efficient, and the blood may become progressively acidic.
That said, CKD is not the only likely explanation. Other causes can coexist with kidney disease and amplify the result. Examples include:
- Lactic acidosis, which can occur when tissues are under stress or not getting enough oxygen. Ketones, which rise in states such as diabetic ketoacidosis or prolonged fasting. Toxins, including certain ingestions that alter blood chemistry and increase acid load.
These causes matter because they can coexist with CKD. A person with chronic kidney disease may have a high anion gap due to reduced clearance of acids, but another trigger can increase it more. That is why the pattern is considered a diagnostic marker rather than a complete answer. Clinicians use the result to direct the next step in evaluation, not to stop at the number alone.
The underlying theme is metabolic acid load. When the body produces more acid than it can dispose of, or when the kidneys cannot clear what is produced, the balance moves. The anion gap helps reveal that shift early enough to support treatment planning and monitoring.
Correcting the Anion Gap for Albumin
One of the most important adjustments in interpretation is adjusting for albumin. Because serum albumin is a major negatively charged protein in the blood, low albumin can make the anion gap look lower than it truly is. This becomes particularly relevant in sick patients and in people with hypoalbuminemia.
When albumin is low, the measured anion gap may underestimate the amount of acid present. A corrected anion gap adjusts for that effect so the clinician can better estimate the true acid burden. Without this adjustment, a person with CKD and low albumin might appear to have a normal gap even though significant metabolic acidosis is present.
The specific correction method can change, but the principle is the same: lower albumin reduces the apparent gap, so the observed number should be adjusted upward when albumin is below normal. For this reason a good Anion Gap Calculator may include an option for albumin adjustment or, at minimum, remind users to consider it separately.
Albumin correction is especially useful when evaluating acid-base patterns in chronic illness, because hypoalbuminemia can coexist with renal impairment, malnutrition, inflammation, or other conditions that influence blood chemistry. Applying the correction can change how the clinician views the severity and type of acid-base disturbance.
How Clinicians Read the Result
Medical professionals review the anion gap as part of a complete acid-base evaluation. Clinicians look at the resulting number, the bicarbonate measurement, the chloride value, the patient’s overall health condition, and whether there is evidence of electrolyte imbalance or other metabolic issues. The aim is to determine whether the pattern fits an acid-base disorder and what is driving it.
In chronic kidney disease, a high gap may support the presence of acid buildup and worsening declining kidney function. A normal gap does not rule out medically significant acidotic states, especially when bicarbonate is low. It may instead point to normal anion gap metabolic acidosis, which can develop when bicarbonate is lost or substituted with chloride in a way that maintains the measured gap.
That distinction is important because it alters the likely causes and the diagnostic path. For instance, a high gap may prompt clinicians to evaluate uremia, lactic acidosis, ketones, or toxins. A normal gap pattern may lead them to focus more on bicarbonate loss, medication effects, or tubular handling of acid and chloride. Either way, the result shapes diagnosis and treatment planning.
Interpretation also considers adaptive responses into account. The body may alter breathing and water regulation in reaction to acid–base changes. Such compensatory mechanisms can affect symptoms and lab patterns, so the anion gap value should be viewed alongside the rest of the broader clinical picture rather than as a separate answer.
When to Seek Medical Evaluation
Those with chronic kidney disease should obtain medical assessment how to calculate corrected anion gap if they experience signs that could reflect more severe acidosis or a significant electrolyte problem. Concerning symptoms may include shortness of breath, severe fatigue, confusion, queasiness, reduced energy, or a general sense that something is wrong. These symptoms are not directly related to the anion gap, but they can point to a need for quick review of blood test results.
If a recently obtained lab report shows an unexpected anion gap, especially along with low bicarbonate or evidence of worsening kidney status, it should be discussed with a clinician. The same is true if there is known renal impairment and symptoms are shifting. In some cases, the issue may be minimal and monitored through observation. In others, it may point to a more serious acid-base disorder that needs care.
Do not rely on a calculator alone if symptoms are present. The lab test result is one piece of the picture, and clinical evaluation is needed to link the value to the person’s condition. The most important step is understanding whether the result represents a consistent ongoing pattern or a new and potentially concerning shift in acid-base balance.
FAQ
What is the anion gap in chronic kidney disease?
The anion gap in chronic kidney disease is a derived blood value used to help assess acid-base balance. It can show whether there is a buildup of unmeasured anions related to acid retention, metabolic acidosis, or other causes. In CKD, it is often used as a guide to help interpret kidney-related blood chemistry changes.
Why does chronic kidney disease cause a high anion gap?
Chronic kidney disease can cause a high anion anion gap in chronic kidney disease gap because reduced kidney function leads to retention of acids and other waste substances. This buildup, often called uremia, increases the number of unmeasured acids in the blood and can result in high anion gap metabolic acidosis. Other problems such as lactic acidosis, ketones, or toxins can also play a role.
Can the anion gap be normal in chronic kidney disease?
Yes. The anion gap can be normal in chronic kidney disease, especially when the acid-base pattern is normal anion gap metabolic acidosis or when albumin is low and the result has not been corrected. A normal value does not exclude acidosis, so the full set of lab values and the patient’s overall condition need to be reviewed.
How do you calculate the anion gap from lab values?
The most common calculation is sodium minus the total of chloride and bicarbonate: anion gap = sodium − (chloride + bicarbonate). Some formulas also include potassium. An Anion Gap Calculator can do the math for you from the available electrolytes and help minimize mistakes when reviewing the electrolyte panel.
Why is albumin correction important when interpreting the anion gap?
Albumin correction is important because serum albumin carries a negative charge, and low albumin can make the anion gap appear falsely low. In people with hypoalbuminemia, the measured value may fail to show an underlying acid problem unless a corrected anion gap is used. This adjustment improves clinical interpretation and helps show the true acid burden.